The NCCPA™ PANCE Cardiovascular System Content Blueprint (current edition) lists the following topics under congenital heart disease:
Congenital heart disease can be divided into two categories: cyanotic and noncyanotic
Congenital Heart Disease Quick Cram
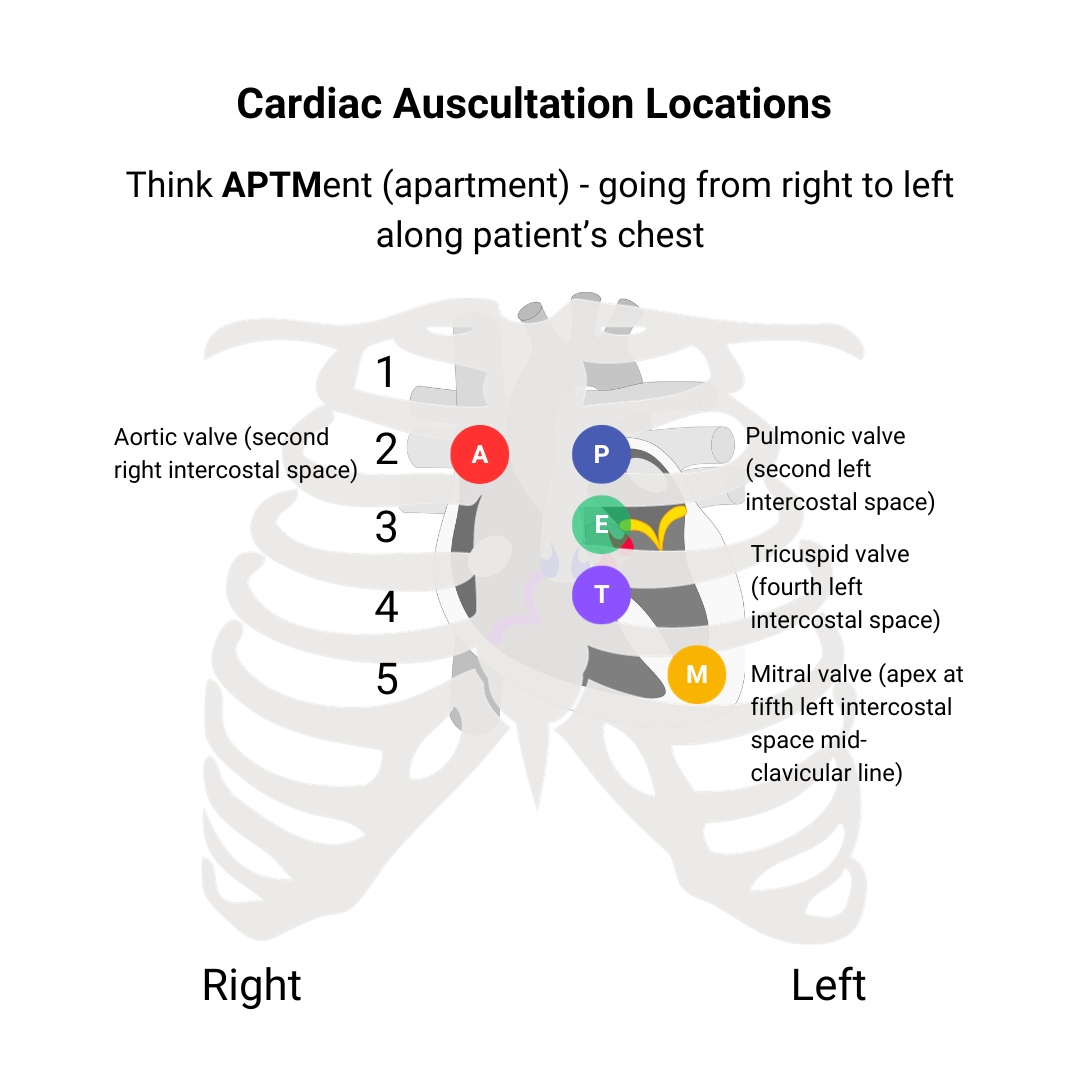
| Atrial septal defect | Systolic murmur heard best at the upper left sternal border with a wide, fixed, split s2 |
| Coarctation of the aorta | Systolic murmur heard best over the left interscapular back; arm BP higher than leg BP with weak, delayed femoral pulses. Rib notching on x-ray |
| Patent ductus arteriosus | A rough, continuous "machinery murmur" at the upper left sternal border (pulmonary area) |
| Patent foramen ovale | Young patient with unexplained stroke or TIA |
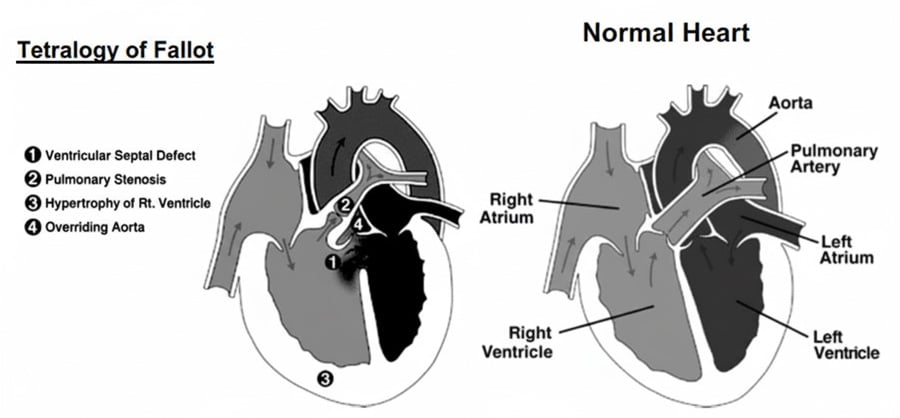
| Tetralogy of Fallot | Failure to thrive. "tet spells," baby with cyanosis and loss of consciousness with crying
Four features: PROVe
|
| Transposition of the great vessels | Severe cyanosis within hours to days of birth, often unresponsive to oxygen therapy (differentiates from pulmonary causes). Diagnosis confirmed with echocardiography, showing parallel great vessels |
| Ventricular septal defect | Loud, harsh, pansystolic murmur at the lower left sternal border |
Non Cyanotic heart defects
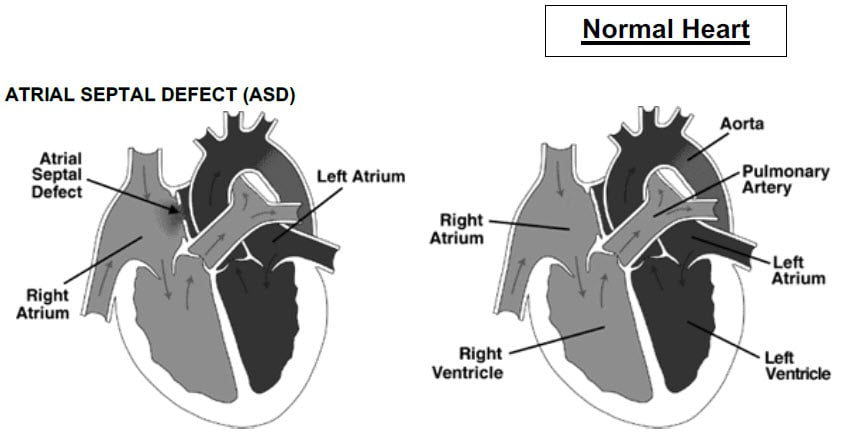
| Atrial septal defect | Patient will present as → a 30-year-old woman with no significant past medical history presents to the clinic with complaints of increasing shortness of breath and palpitations, particularly during exercise. She also mentions a recent episode of fainting after climbing a flight of stairs. On examination, you note a grade III/VI systolic ejection murmur is present in the 2nd left intercostal space (pulmonic position) with an early to mid-systolic rumble and fixed splitting of the second heart sound (S2) during inspiration and expiration. She has no signs of heart failure. A chest X-ray reveals a prominent pulmonary artery, and an EKG shows a right bundle branch block. An echocardiogram is performed, which demonstrates a large secundum atrial septal defect (ASD) with a significant left-to-right shunt. It also shows right atrial and right ventricular enlargement with normal pulmonary artery pressure. Echocardiography is diagnostic, so cardiac catheterization is not needed. She is referred to cardiology for percutaneous (transcatheter) device closure of the defect to prevent long-term complications such as atrial arrhythmias, pulmonary hypertension and right heart failure.
Noncyanotic Opening in the interatrial septum (a true tissue gap, unlike the flap of a PFO). Ostium secundum is most common (about 75 to 80%); ostium primum goes with Down syndrome and left axis deviation; sinus venosus goes with anomalous pulmonary venous return Physical Exam: Wide, fixed, and split second heart sound (S2). Systolic ejection murmur at the second left intercostal space with an early to mid-systolic rumble. Usually asymptomatic in childhood; exercise intolerance, atrial arrhythmias and paradoxical embolism appear in adults. Diagnosis: Echocardiography - DEFINITIVE DIAGNOSIS will demonstrate a septal defect
Treatment:
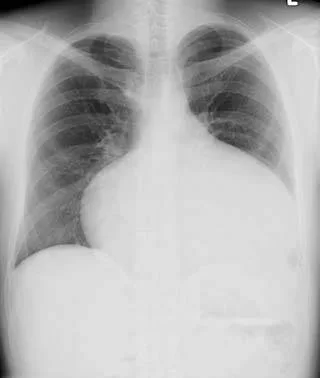 Abnormal chest X-ray as seen in a patient of Atrial septal defect. Image: WikiSysop, CC BY-SA 3.0, via Wikimedia Commons. |
| Coarctation of aorta | Patient will present as → a 15-year-old boy, previously healthy, presents to your clinic with complaints of leg fatigue and cramping after physical activities, especially when climbing stairs or playing soccer. He also reports frequent headaches. On examination, you find a significant discrepancy in blood pressure between his arms and legs, with higher readings in the arms. Additionally, there is a notable delay in the femoral pulse compared to the brachial pulse. Auscultation reveals a systolic murmur best heard in the left interscapular region. His medical history is unremarkable, and there are no known congenital heart defects in the family. However, he mentions that he has always been slightly shorter than his peers. CXR is performed, demonstrating a “figure of 3 sign” and an echocardiogram suggests a narrowing of the aorta distal to the left subclavian artery, consistent with coarctation of the aorta. A CT angiogram is ordered for further assessment, confirming the diagnosis and identifying the extent of the narrowing. The cardiology team is consulted for management, which at his age is usually transcatheter stent placement for a discrete narrowing (surgical repair for long or complex segments). The patient is also started on antihypertensive medication to control his blood pressure until definitive treatment can be arranged.
Noncyanotic - Typically found just after the vessels are given off to the left arm. This is a cause of high blood pressure, as the kidneys do not "see" as high of a blood pressure as they would like
Systolic ejection murmur heard best over the left interscapular back (continuous if large collaterals); an ejection click points to a bicuspid aortic valve A bicuspid valve is seen in about half or more of cases; also associated with Turner syndrome (45,X) (karyotype any girl with coarctation) and cerebral berry aneurysm DX: Four-extremity blood pressures (arm–leg systolic gradient >20 mm Hg) → Definitive Diagnosis is by echocardiography or by CT or MR angiography
TX: Treatment is balloon angioplasty with stent placement or surgical correction
|
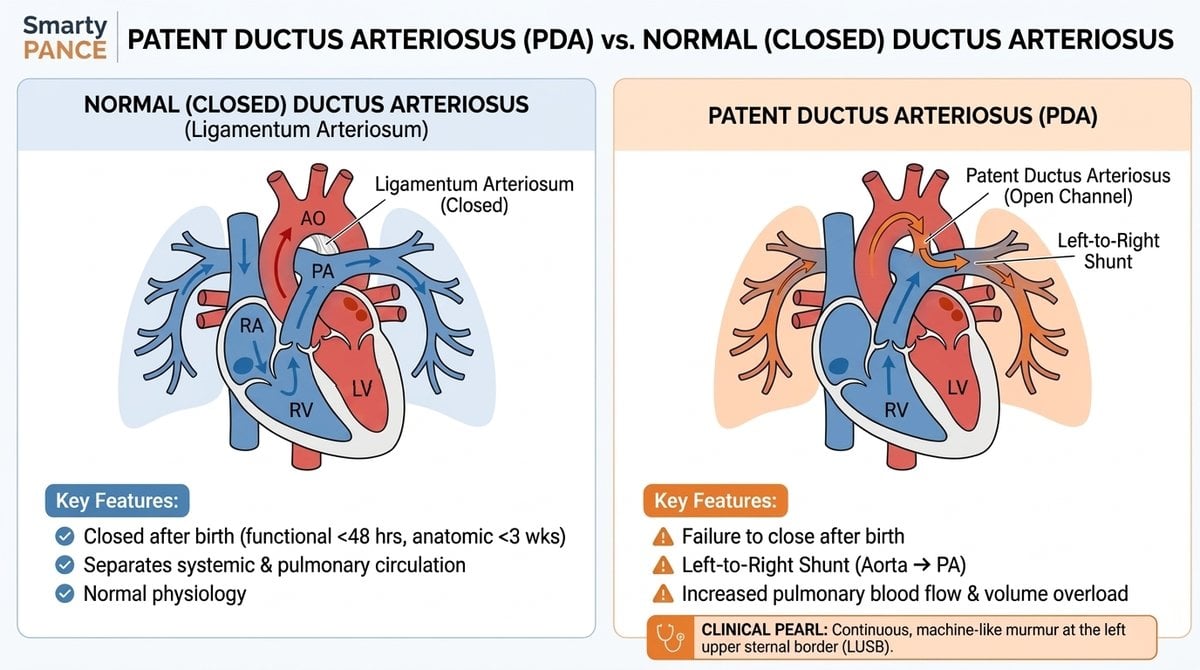
| Patent ductus arteriosus | Patient will present as → a 4-day-old former 30-week preterm infant with a soft systolic murmur at the left upper sternal border. He is on room air, feeding and gaining weight, with normal pulses. Echo shows a small patent ductus arteriosus. He is managed expectantly — most preterm ducts close on their own. Patient will present as → a 6-day-old former 27-week preterm infant who cannot wean from the ventilator. He has a hyperdynamic precordium, bounding pulses, and a continuous “machinery” murmur at the left upper sternal border with a wide pulse pressure. Echo confirms a hemodynamically significant patent ductus arteriosus. He is treated with ibuprofen.
Noncyanotic - Ductus arteriosus is a normal fetal structure => If it remains open, it's called a patent ductus arteriosus
Diagnose: Echocardiogram Treatment: ⚠️ Expectant management is the default in the preterm infant — most close spontaneously
|
| Patent foramen ovale | Patient will present as → a 38-year-old female presents to the clinic with a history of transient ischemic attack (TIA). She reports a sudden onset of speech difficulties and right-sided weakness that resolved completely within an hour. She has no prior history of strokes or TIAs, and her medical history is unremarkable. She does not smoke and has no family history of cardiac or thromboembolic diseases. On examination, she is neurologically intact. A thorough cardiovascular examination reveals no abnormalities, and her EKG is normal. Given her age and the unexplained nature of the TIA, a workup for cryptogenic stroke (stroke of undetermined etiology) is initiated. A transthoracic echocardiogram (TTE) with a bubble study is performed, showing bubbles passing from the right to the left atrium, indicating the presence of a patent foramen ovale. To further evaluate the PFO and rule out other structural heart diseases, a transesophageal echocardiogram (TEE) is conducted, confirming the diagnosis. The patient is counseled about the potential risks and benefits of PFO closure versus medical management. After discussing her options, she opts for medical management with antiplatelet therapy to reduce the risk of future thromboembolic events. 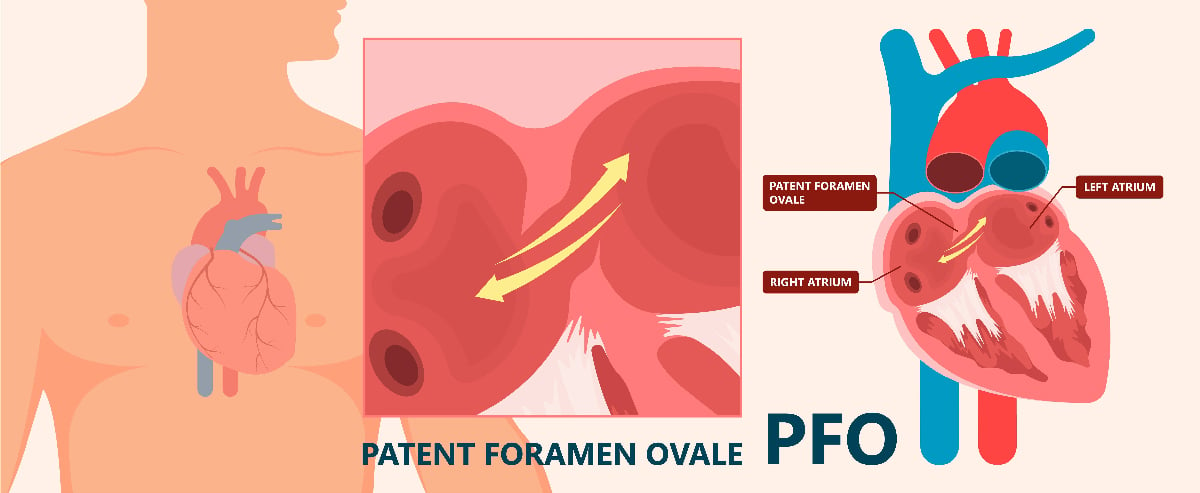 Credit @AdobeStock A patent foramen ovale (PFO) is a persistent opening between the left and right atria of the heart, which normally closes shortly after birth. It is a common finding, present in up to 25% of the general population
DX: Transesophageal echocardiography (TEE) with bubble study is the most definitive test (a contrast bubble transthoracic echo is usually done first), showing the passage of bubbles from the right atrium to the left atrium
TX: Treatment of PFO depends on the presence of symptoms and the risk of complications:
|
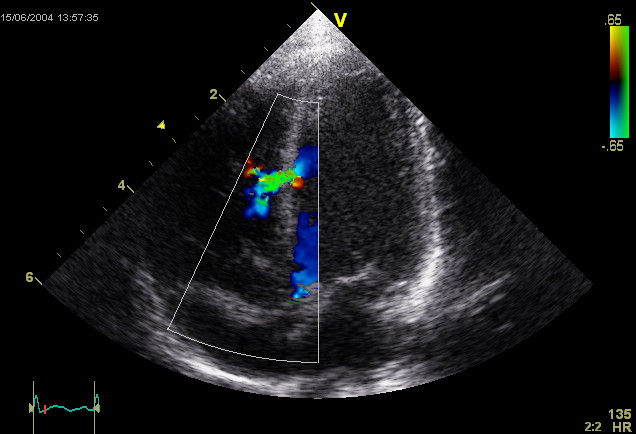
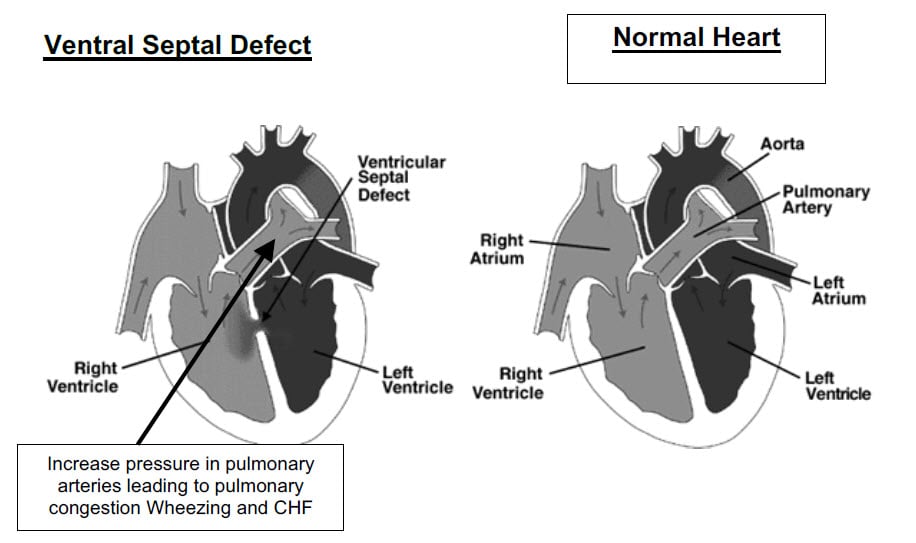
| Ventricular septal defect | Patient will present as → a 4-year-old boy who is brought to your office by his parents because he gets tired very easily and cannot keep up with the other children. On exam, you hear a loud, harsh, holosystolic murmur at the left lower sternal border without radiation to the axillae. An echocardiogram is performed and reveals a ventricular septal defect (VSD), with results seen here.
Noncyanotic - VSD is the most common pathologic murmur in childhood
PE: Loud, harsh, holosystolic murmur, left to right - heard best at the lower left sternal border
DX: Echocardiogram Treatment: small VSDs are observed (many close on their own, most within the first 2 years; the smaller the defect, the louder the murmur); large VSDs with heart failure get diuretics and high-calorie feeds, then surgical closure in infancy; never close once Eisenmenger syndrome develops 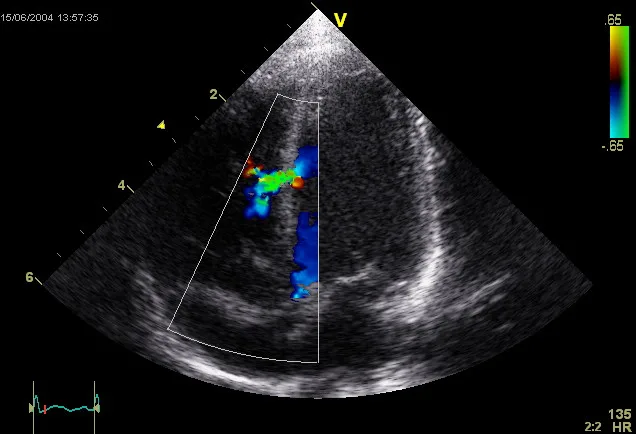 Echocardiogram of a ventricular septal defect. Image: Kjetil Lenes, Public domain, via Wikimedia Commons. |

Cyanotic defects
| Tetralogy of Fallot | Patient will present as → a 2-week-old newborn brought to the ER by his mom who reports a sudden loss of consciousness during feeding and with crying. She also has noticed that the infant’s lips have turned blue on three occasions during feeding. His blood pressure is 75/45 mmHg, his pulse is 170/min, and respirations are 44/min. A grade 3/6 harsh systolic ejection murmur is heard at the left upper sternal border. A CXR shows a small boot-shaped heart and decreased pulmonary vascular markings.
Cyanotic Presentation: Difficult feeding, failure to thrive. "tet spells," a baby with cyanosis and loss of consciousness with crying Four features: PROVe
Physical exam: Harsh crescendo-decrescendo systolic ejection murmur at the left upper sternal border with a single S2 (from the right ventricular outflow obstruction, not the VSD)
DX: Echocardiography is the diagnostic modality of choice. This test can clearly define the four abnormalities as well as provide important information about aortic arch anatomy
Chest radiograph: Boot-shaped heart TX: Complete surgical repair (VSD closure + relief of the outflow obstruction), usually electively at about 3 to 6 months of age; ductal-dependent newborns get prostaglandin E1 first. Tet spell: knee-to-chest, oxygen, IV fluids, morphine, then an IV beta-blocker or phenylephrine if it persists. Late: pulmonary regurgitation and arrhythmias 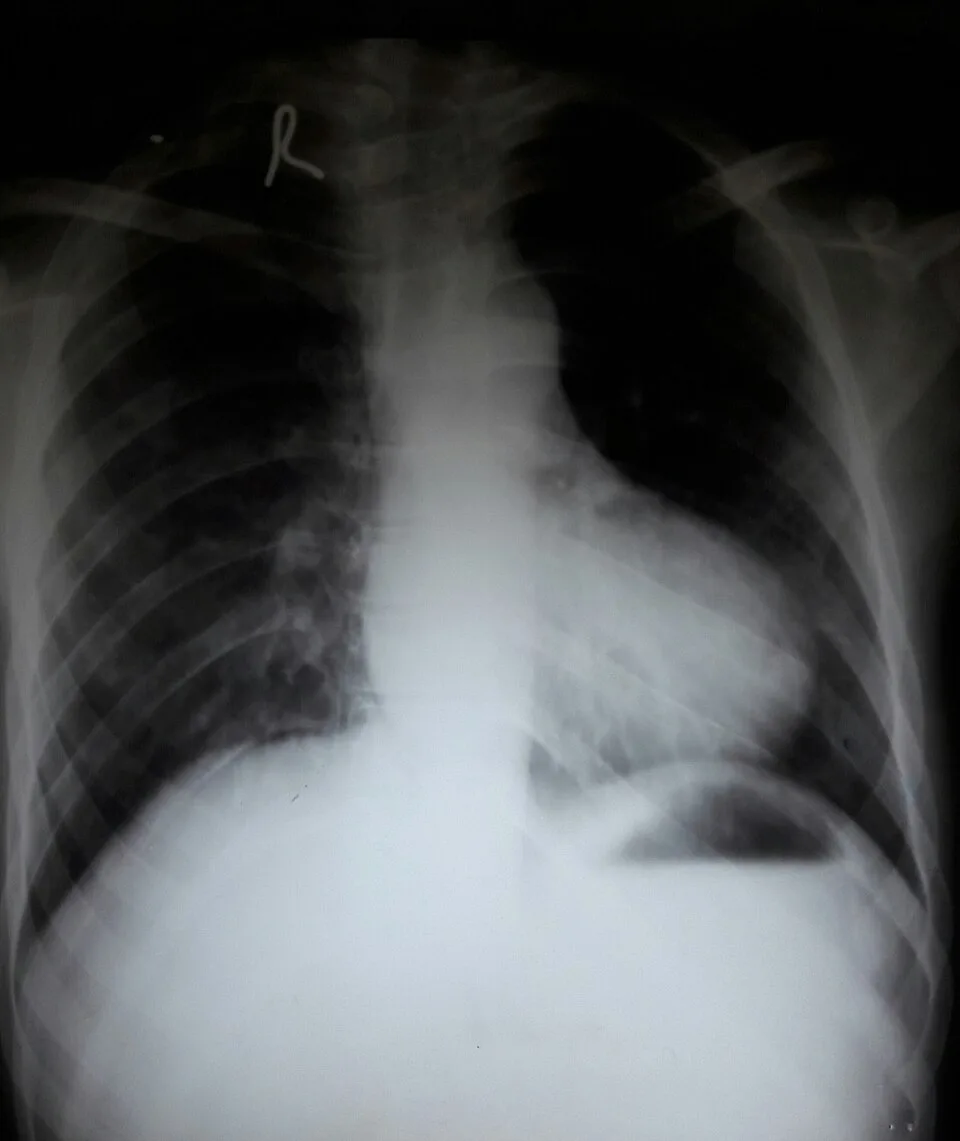 CXR from a patient with tetralogy of Fallot (TOF). The white shadow is the cardiac silhouette. It looks like a wooden boot. Image: Medicalpal, CC BY-SA 4.0, via Wikimedia Commons. |
| Transposition of the great vessels | Patient will present as → a 3-day-old male neonate presents with cyanosis since birth that worsens with crying. Oxygen saturation is 75% on room air. Exam reveals a loud single S2 without a murmur. Chest X-ray shows an “egg-on-a-string” heart, and echocardiography confirms transposition of the great vessels (TGV) with a PDA and ASD providing limited blood mixing. Management includes prostaglandin E1 infusion to maintain ductal patency, balloon atrial septostomy, and definitive arterial switch surgery. The infant is monitored in the NICU and requires long-term cardiology follow-up. Transposition of the great vessels (TGV) is a congenital heart defect where the aorta arises from the right ventricle and the pulmonary artery arises from the left ventricle, resulting in two parallel circulatory systems The aorta arises from the right ventricle and the pulmonary artery arises from the left ventricle, resulting in two separate circuits:
Severe cyanosis within the first hours to days of life, often unresponsive to oxygen therapy (differentiates from pulmonary causes), worsening as the ductus arteriosus closes
DX: Postnatal diagnosis is typically made via echocardiogram
TX: Surgery with arterial switch operation (Jatene procedure) performed ideally within the first 1 to 2 weeks of life to correct the defect
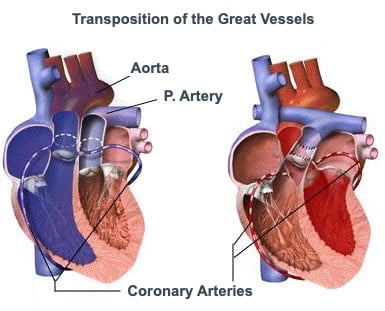 Image by Pezard, CC BY-SA 3.0, via Wikimedia Commons (English captions by Smarty PANCE) |