


Patient will present as → a 4-month-old boy is brought to your office by his parents, who are concerned about his episodes of turning blue, especially during feeding or crying. The parents also report that he seems to get tired more quickly than other infants his age. On examination, you note the baby has a mild cyanotic hue, particularly around his lips and fingertips. The infant's growth is slightly below the expected percentile for his age. Auscultation reveals a harsh systolic ejection murmur best heard at the left upper sternal border. A CXR shows a small boot-shaped heart and decreased pulmonary vascular markings. You suspect a congenital heart defect and order an echocardiogram, which confirms the diagnosis of Tetralogy of Fallot, characterized by four cardiac abnormalities: ventricular septal defect, overriding aorta, pulmonary stenosis, and right ventricular hypertrophy. You generate an urgent referral to a pediatric cardiologist for further management, including surgical intervention to correct the defect and improve oxygenation, which is usually done electively at about 3 to 6 months of age (sooner after significant spells) to prevent complications and promote normal development.

Cyanotic heart disorder that is characterized by four defects (tetra = 4) that together cause oxygen-deficient blood to flow out of the heart and into the rest of the body
Four features: PROVe
- P ulmonary Stenosis
- R ight ventricular hypertrophy
- O verriding aorta
- V entricular septal defect
The pulmonary stenosis causes a right to left shunt through the VSD, thereby causing cyanosis.
- TET SPELLS: hypercyanotic episodes that develop during crying or feeding; the murmur gets softer during a spell because less blood crosses the narrowed outflow tract
- The severity of the right ventricular outflow obstruction sets how cyanotic the child is (mild obstruction = acyanotic "pink tet")
- Associations: 22q11.2 deletion (DiGeorge) syndrome (test every child with TOF), trisomy 21; right aortic arch in about 25%
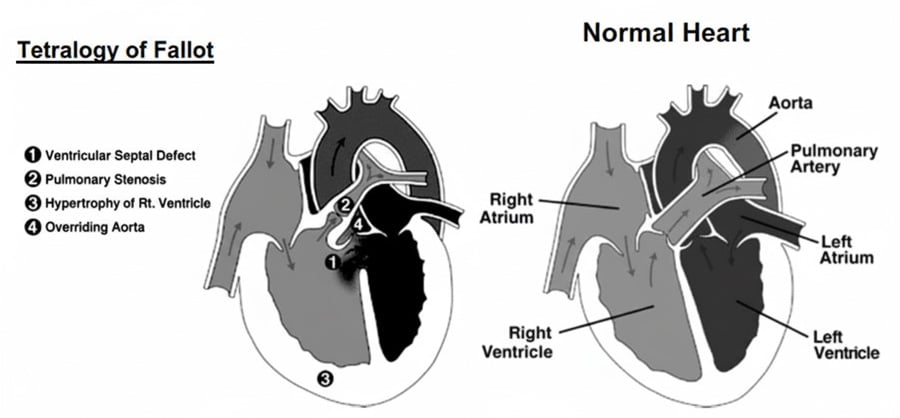
The murmur is classically described as a harsh systolic ejection murmur heard best at the left upper sternal border with a single S2. It comes from the right ventricular outflow obstruction, not the VSD (which is usually silent)
- The murmur is usually present at birth
- The murmur gets softer or disappears during a tet spell as outflow obstruction worsens
- Newborn pulse-oximetry screening may pick up cyanotic lesions; echocardiography confirms the diagnosis
Echocardiography is the diagnostic modality of choice. This test can clearly define the four abnormalities as well as provide important information about aortic arch anatomy
- A chest x-ray classically shows a boot-shaped heart
- EKG shows right axis deviation and right ventricular hypertrophy (right atrial enlargement may be present). After repair, check QRS width yearly; a QRS over 180 ms marks higher risk of sudden cardiac death
- Cardiac catheterization may be required in some patients to fully define the anatomy
- Squatting decreases the cyanosis in tetralogy of Fallot because it raises systemic vascular resistance and reduces right-to-left shunting
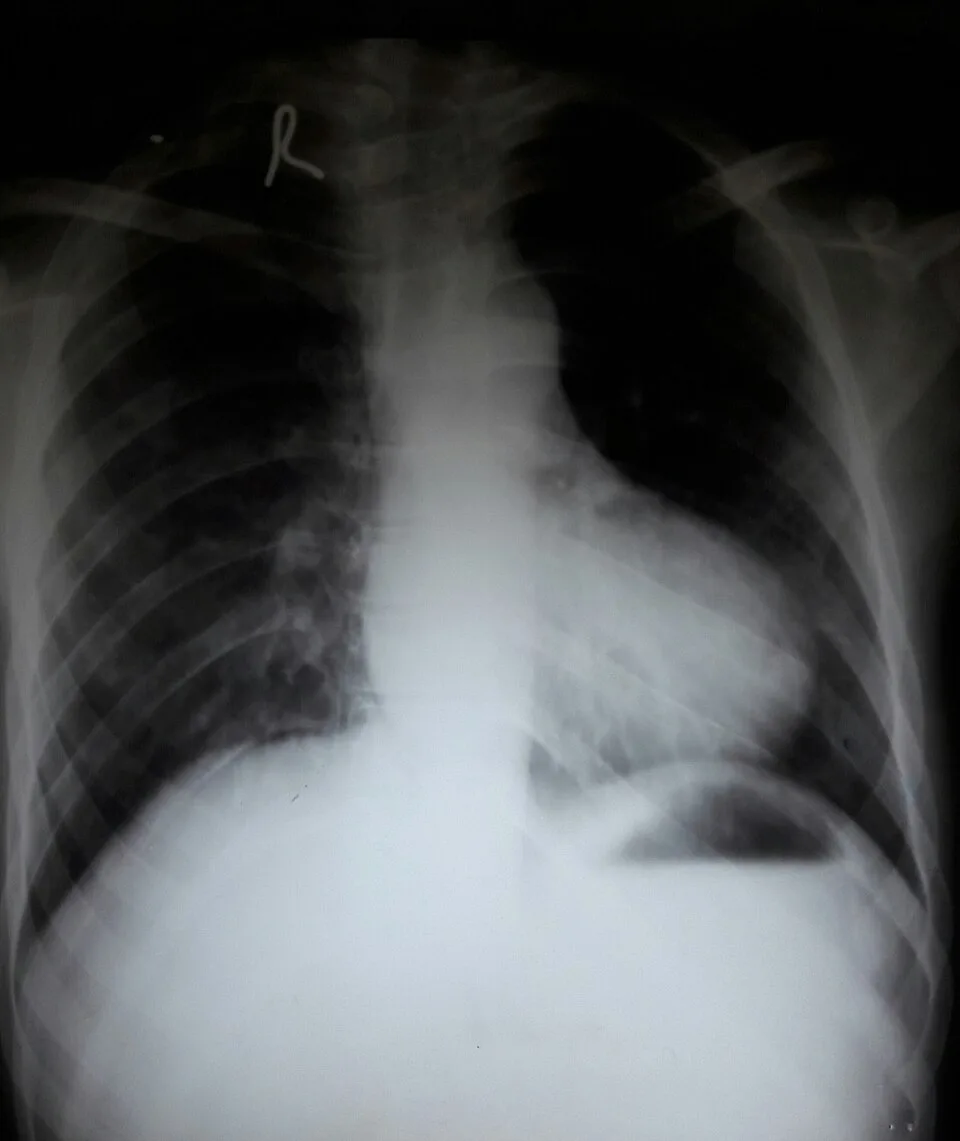
CXR from a patient with tetralogy of Fallot (TOF). The white shadow is a cardiac silhouette. It looks like a wooden boot. Image: Medicalpal, CC BY-SA 4.0, via Wikimedia Commons.
Treatment involves complete surgical repair, usually done electively at about 3 to 6 months of age (sooner after significant spells), including patch closure of the VSD and relief of the right ventricular outflow obstruction
- Tet spell: knee-to-chest position and calm the infant, then oxygen, IV fluid bolus and IV morphine; if the spell persists, an IV beta-blocker (propranolol or esmolol) or phenylephrine to raise systemic vascular resistance; refractory spells need sedation, intubation or urgent surgery
- Severely cyanotic, ductal-dependent newborns: prostaglandin E1 to keep the ductus open, then early repair or palliation (a modified Blalock-Taussig shunt or a ductal/outflow stent)
- Twenty-year survival rates after surgery are above 80%. The most common causes of death are sudden cardiac death and heart failure
- Complications after surgery include arrhythmias, pulmonary regurgitation (most common; can dilate the right ventricle), residual outflow obstruction, and heart failure. Lifelong congenital heart follow-up; pulmonary valve replacement when regurgitation causes symptoms, right ventricular enlargement or dysfunction, or arrhythmias
 Osmosis |
|
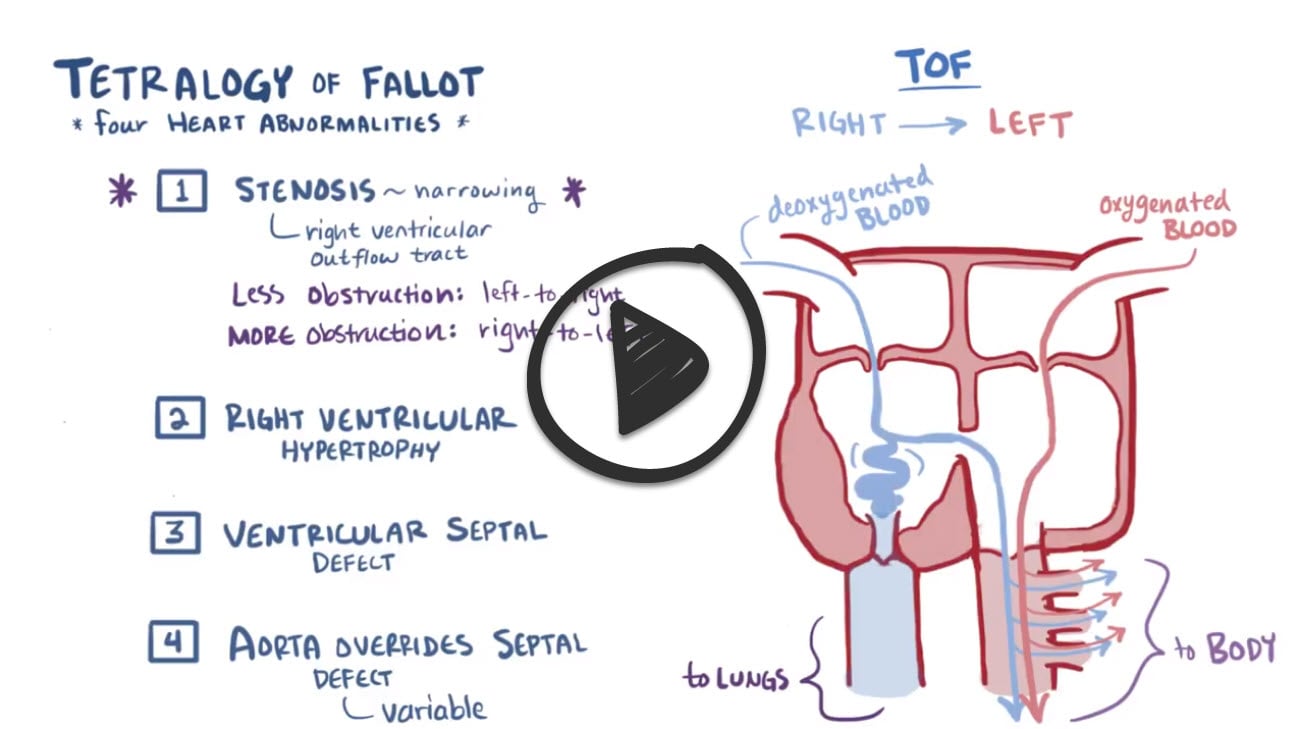 |
Tetralogy of Fallot is a congenital birth defect of the heart leading to cyanosis. It presents with up to 4 different heart defects, and is the most common cause of blue baby syndrome. The four pathologies in this disease are pulmonary infundibular stenosis, right ventricular hypertrophy, overriding aorta, and ventricular septal defect.
Play Video + QuizQuestion 1 |
DiGeorge (22q11.2 deletion) syndrome | |
Fragile X syndrome Hint: Fragile X syndrome causes intellectual disability and mitral valve prolapse, not cyanotic heart disease. | |
Marfan syndrome Hint: Marfan syndrome is linked to aortic root dilation and mitral valve prolapse. | |
Turner syndrome Hint: Turner syndrome is linked to coarctation of the aorta and bicuspid aortic valve. | |
Williams syndrome Hint: Williams syndrome is linked to supravalvular aortic stenosis. |
Question 2 |
Cardiac catheterization Hint: Catheterization is invasive and is reserved for selected cases where anatomy (such as coronary or pulmonary artery branches) is still unclear after echo. | |
Cardiac MRI Hint: Cardiac MRI is mainly used after repair to measure right ventricular size and pulmonary regurgitation, not for the first diagnosis in an infant. | |
Chest CT angiography Hint: CT angiography adds radiation and is not the first confirmatory test; it may help define vessels in selected cases. | |
Electrocardiography Hint: The ECG shows right axis deviation and right ventricular hypertrophy, which supports the diagnosis but cannot define the anatomy. | |
Transthoracic echocardiography |
Question 3 |
Intravenous adenosine Hint: Adenosine terminates supraventricular tachycardia and has no role in a hypercyanotic (tet) spell. | |
Intravenous furosemide Hint: Diuresis lowers preload and systemic vascular resistance, which worsens the right-to-left shunt during a tet spell. | |
Knee-to-chest positioning | |
Sublingual nitroglycerin Hint: Vasodilators lower systemic vascular resistance, increasing the right-to-left shunt and worsening cyanosis. | |
Synchronized cardioversion Hint: A tet spell is not a tachyarrhythmia, so cardioversion is not indicated. |
Question 4 |
Balloon atrial septostomy Hint: Septostomy enlarges the atrial opening to improve mixing in transposition of the great arteries; it does not treat tetralogy. | |
Complete surgical repair in infancy (VSD closure and relief of the outflow obstruction) | |
Heart transplantation Hint: Transplantation is not used for tetralogy, which has excellent results with complete repair. | |
Lifelong oral propranolol without surgery Hint: Propranolol can reduce spells while awaiting surgery, but it does not correct the defect. | |
Routine modified Blalock-Taussig shunt followed by repair in adolescence Hint: A shunt is a palliative bridge for selected sick neonates; routine staged repair has been replaced by early complete repair. |
Question 5 |
Aortic stenosis Hint: Aortic stenosis loads the left ventricle and is not the typical late problem after tetralogy repair. | |
Coarctation of the aorta Hint: Coarctation is not part of tetralogy and does not dilate the right ventricle. | |
Mitral regurgitation Hint: Mitral regurgitation enlarges the left atrium and left ventricle, not the right ventricle. | |
Pulmonary regurgitation | |
Tricuspid stenosis Hint: Tricuspid stenosis is rare and would enlarge the right atrium, not the right ventricle. |
|
List |
References: Merck Manual · UpToDate