

 Lecture

Patient will present as → a 34-year-old woman with a 3-day history of hematuria, dysuria, increased urinary frequency, and nocturia. She has had no fever, chills, or back pain. On examination, she does not look ill. Her temperature is 37.5 ° C. Her abdomen is nontender. There is no CVA tenderness.


To watch this and all of Joe Gilboy PA-C's video lessons you must be a member. Members can log in here or join now.
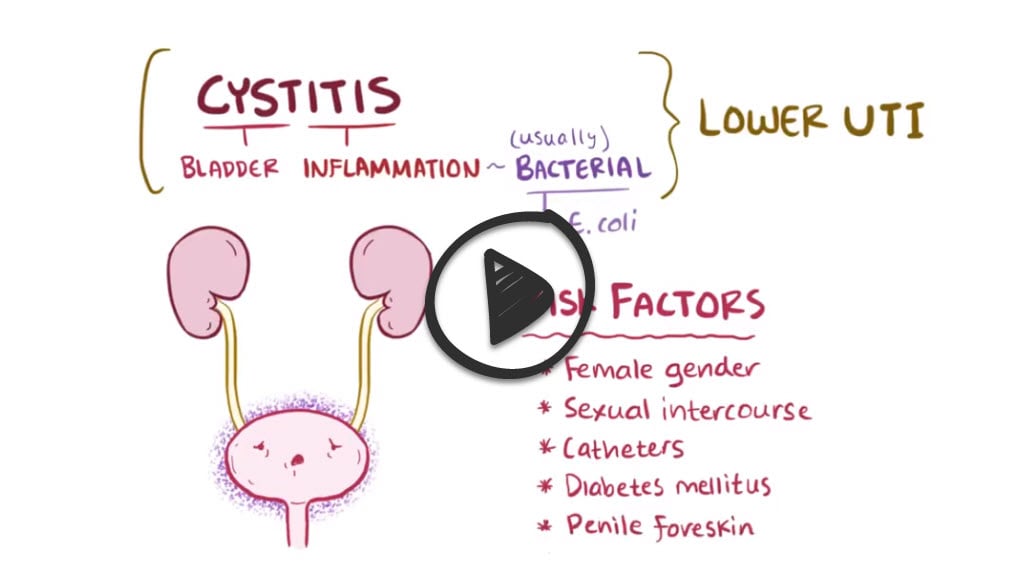
Cystitis is an infection of the bladder
- Characterized by dysuria (painful urination) WITHOUT urethral discharge
- frequent urination/urgency, +/- hematuria
- Abdominal or suprapubic pain
- New-onset incontinence (in toilet-trained children)
- Absence of fever, chills, or flank pain
- The most common cause is E. coli (80%) - gram-negative - Klebsiella; Proteus; Enterobacter; Citrobacter
- Gram-positive bacteria: Enterococcus; S. saprophyticus, second most common, esp. in young individuals who are biologically female, sexually active
- Common in women, in whom cases of uncomplicated cystitis are often preceded by sexual intercourse (honeymoon cystitis)
- In men, a bacterial infection of the bladder is usually complicated and usually results from ascending infection from the urethra or prostate or is secondary to urethral instrumentation
- The most common cause of recurrent cystitis in men is chronic bacterial prostatitis
Urine dipstick ⇒ nitrite, leukocyte esterase (enzyme created by white blood cells)
- Urinalysis: pyuria (white blood cells in urine), bacteriuria, +/− hematuria, +/− nitrites
- Urine culture (gold standard)
- > 100,000 CFU/mL (women)
- > 1000 CFU/mL men or cath patients
- → takes 24 h to obtain results
- Imaging studies are not required for most women with UTIs and are warranted only if pyelonephritis, recurrent infections, or concern for anatomic abnormalities
Uncomplicated UTI (adolescents and adults who are nonpregnant, non-diabetic, afebrile, immunocompetent, and without genitourinary anatomic abnormalities)
- Trimethoprim-sulfamethoxazole (TMP-SMZ; Bactrim): 160/800 mg PO BID × 3 days, best where the resistance of E. coli strains <20%
- A 5-day course of nitrofurantoin is also first-line and is the choice if the patient is allergic to TMP-SMZ or local E. coli resistance to TMP-SMZ is >20%
- Fluoroquinolones (e.g., ciprofloxacin) are not first-line for uncomplicated cystitis because of adverse effects and resistance; reserve them for when other agents cannot be used or for more serious infections
- Fosfomycin (Monurol): 3 g PO single dose (expensive)
The urinary tract topical analgesic phenazopyridine (Pyridium) 100–200 mg TID produces rapid relief of symptoms and should be offered to patients with more than minor discomfort; it is available over the counter. This medication is not a substitute for definitive treatment. This medication also may alter urinalysis but not the urine culture.
Treatment of uncomplicated UTIs reduces morbidity, but the risk of recurrence stays the same
- All pregnant women with bacteriuria should be treated
- Asymptomatic bacteriuria is commonly seen in the geriatric population and no treatment is needed as long as the patient is not diabetic or has no structural abnormalities of the genitourinary tract.
Treatment update

"You'll see more emphasis on limiting the use of quinolones. It's coming from more concerns about "collateral damage" leading to resistance...and warnings of tendon rupture, peripheral neuropathy, etc. Watch for situations where you may want to bench quinolones. Urinary tract infections. Use nitrofurantoin or trimethoprim/sulfamethoxazole (TMP/SMX) for most UNcomplicated UTIs. Nitrofurantoin used to be discouraged in renal insufficiency...but the new thinking is that it's safe and effective if CrCl > 30 mL/min. Also consider a cephalosporin (cephalexin, etc) or Monurol(fosfomycin)...depending on the bug causing the UTI. Save quinolones (ciprofloxacin, etc) for COMPLICATED UTIs when appropriate...such as patients with obstruction (kidney stones, etc) - Prescriber's Letter "
Lower UTI in pregnancy
- Nitrofurantoin is a preferred empiric choice (TMP-SMX is generally avoided in the first trimester). Cefpodoxime, amoxicillin-clavulanate, and fosfomycin are also appropriate options. Tailor therapy to the urine culture
- Fluoroquinolones are NOT safe during pregnancy and are usually avoided in the treatment of children.
- TMP-SMX use in pregnancy is NOT desirable (especially in 3rd trimester) but is appropriate in some circumstances
Postcoital UTI: low-dose nitrofurantoin (50 to 100 mg orally postcoitally or at bedtime) or cephalexin (250 to 500 mg orally postcoitally or at bedtime) may reduce the frequency of UTI in sexually active women
Complicated UTI (diabetes, febrile, immunocompromised patient, recurrent UTIs): Extend course to 7–10 days of treatment with antibiotic chosen based on culture results; may begin with fluoroquinolone, TMP-SMX, or cephalosporin while awaiting results (avoid using nitrofurantoin for complicated UTI)
- Cephalosporin x 14 days are the first-line oral agent in the treatment of UTI in children without genitourinary abnormalities
- First-generation cephalosporin (Keflex 50-100 mg/kg BID) for low risk of renal involvement
- Second-generation (cefuroxime) or third-gen (cefixime, cefdinir, ceftibuten) for those with a high likelihood of renal involvement
 Osmosis |
|
 |
 Fluoroquinolones are a family of broad spectrum antibiotic drugs that commonly end with suffix floxacin like ciprofloxacin and moxifloxacin. These drugs are bactericidal and eradicate bacteria by interfering with DNA replication. Fluoroquinolones inhibit topoisomerase II enzymes including bacterial DNA gyrase. These enzymes cut both strands of the DNA helix in order to unwind DNA tangles and supercoils which is necessary for proper DNA replication. These drugs are broad spectrum antibiotics that play an important role in the treatment of serious bacterial infections, especially against gram negative rod infections. Fluoroquinolones, especially ciprofloxacin, is commonly used in the treatment of urinary tract infections and also used in the treatment of Pseudomonas and Neisseria infections. Products containing multivalent cations, like aluminum or magnesium containing antacids, result in drastic reduction of oral absorption and should not be taken together. In general, adverse effects to fluoroquinolones are generally mild to moderate and include diarrhea, skin rashes, and headaches. On occasion, more serious adverse effects can occur. Fluoroquinolones can damage cartilage and ligaments and can cause spontaneous tendon rupture. They are also associated with fibromyalgia like symptoms including leg cramps and myalgias in children. Because they can damage cartilage and ligaments, they are not recommended for use in pregnant women or children and are considered a teratogen.
| Fluoroquinolones Antibiotics | Play Video + Quiz |
| Fluoroquinolones Toxicities | Play Video + Quiz |
Trimethoprim

Trimethoprim is a bacteriostatic antibiotic that inhibits bacterial dihydrofolate reductase. This enzyme normally reduces dihydrofolic acid to tetrahydrofolic acid using NADPH as an electron donor. Inhibition of this enzyme leads to inhibition of the synthesis of tetrahydrofolic acid, which is essential in the synthesis of nucleotides for DNA synthesis. Trimethoprim is commonly used in combination with sulfamethoxazole, which is a sulfonamide antibiotic that is a competitive antagonist of PABA metabolite and causes inhibition of the enzyme dihydropteroate synthetase, also in the folic acid synthesis pathway. Using these drugs in combination causes sequential block of folate synthesis and has a synergistic effect. Trimethoprim is commonly used in the treatment of recurrent urinary tract infections and is also effective against Shigella and Salmonella. Specifically, TMP-SMX is used for both prophylaxis and treatment of Pneumocystis jiroveci. The use of this antibiotic can cause a decrease in red and white blood cell counts due to lowering of folic acid levels in the individual. This side effect can be alleviated with the administration of leucovorin, also called folinic acid. Leucovorin is a derivative of tetrahydrofolic acid that has activity equivalent to that of folic acid. Leucovorin does not require dihydrofolate reductase for activation and is therefore not inhibited by drugs like trimethoprim.
Play Video + QuizSulfonamides
 Sulfonamides are a group of bacteriostatic antibiotics that contain a sulfonamide moiety. These drugs have a wide spectrum encompassing most Gram positive and many Gram negative organisms including nocardia and Chlamydia. Sulfonamides are structural analogs and competitive antagonists of para-aminobenzoic acid (PABA) and compete with para-aminobenzoic acid (PABA) for incorporation into folic acid. Incorporation of sulfonamides causes inhibition of the enzyme dihydropteroate synthetase in the folic acid synthesis pathway. Because folic acid is necessary for vital cell functions like DNA synthesis, bacteria that are deprived of folate will eventually die. Commonly used sulfonamides include sulfamethoxazole, sulfisoxazole, and sulfadiazine. The overall incidence of adverse drug reactions is approximately 3% and common symptoms include skin reactions ranging from mild rashes to life-threatening Stevens Johnson syndrome, liver and kidney injury, lung reactions and blood reactions. Common sulfa drugs include sulfasalazine, sulfonylureas, thiazide diuretics, acetazolamide, furosemide, celecoxib, and probenecid. Sulfonamides are also associated with causes hemolysis of red blood cells in G6PD deficiency individuals. Additionally, they can cause nephrotoxicity, and photosensitivity. In the plasma, sulfonamides can bind to albumin and displace bilirubin to cause kernicterus in infants and can also displace warfarin, causing unexpected increases in clotting time and uncontrolled bleeding in individuals on warfarin therapy.
| Sulfonamides Mechanisms | Play Video + Quiz |
| Sulfonamides Side Effects | Play Video + Quiz |
| Sulfa Drug Allergies | Play Video + Quiz |
Question 1 |
Phenazopyridine (Pyridium) | |
Oxybutynin (Ditropan) Hint: Oxybutynin is an antispasmodic and anticholinergic used in the treatment of overactive bladder. | |
Finasteride (Proscar) Hint: Finasteride is an alpha-blocker used in the treatment of benign prostatic hypertrophy. | |
Imipramine (Tofranil) Hint: Imipramine is an anticholinergic used to treat childhood enuresis. |
Question 2 |
Ciprofloxacin Hint: A fluoroquinolone treats symptomatic urinary tract infection. Asymptomatic bacteriuria in an older adult should not be treated; antibiotics add adverse effects and resistance without benefit. | |
Trimethoprim-sulfamethoxazole Hint: Trimethoprim-sulfamethoxazole is a first-line drug for acute cystitis, but this patient has no urinary symptoms and does not need treatment. | |
Cephalexin Hint: Cephalexin is an option for symptomatic cystitis, not for asymptomatic bacteriuria, which is common and harmless in nursing home residents. | |
No antimicrobial therapy | |
Nitrofurantoin Hint: Nitrofurantoin treats uncomplicated cystitis. Bacteriuria without symptoms is not cystitis and is not treated in older adults. |
Asymptomatic bacteriuria (bacteria in the urine without urinary symptoms) is not treated in older adults, including nursing home residents. It is very common in this population, and antibiotics do not prevent symptomatic infection or sepsis; they only add adverse effects, Clostridioides difficile infection, and resistant organisms. The same applies to patients with diabetes and to patients with an indwelling catheter.
Nonspecific findings such as delirium, falls, or a change in urine odor or cloudiness, without fever or urinary symptoms, are not reasons to treat. Screening for and treating asymptomatic bacteriuria is reserved for pregnancy and for patients about to undergo a urologic procedure expected to cause mucosal bleeding.
Question 3 |
Order urine culture and sensitivity Hint: A culture of a contaminated specimen will grow mixed vaginal flora and will be hard to interpret. | |
Obtain renal ultrasound Hint: Imaging is not part of the evaluation of simple dysuria in a young woman. | |
Repeat urinalysis with a clean catch sample | |
Refer to a nephrologist Hint: Nothing here suggests kidney disease needing specialist referral. |
Question 4 |
Fever and chills Hint: Signs of systemic toxicity, such as fever and chills, are absent in acute cystitis. | |
CVA tenderness Hint: CVA tenderness and flank pain are associated with acute pyelonephritis. | |
Flank pain Hint: See B for explanation. | |
Frequency and dysuria |
Question 5 |
Doxycycline (Vibramycin) Hint: Doxycycline is contraindicated during pregnancy because of dental staining in the exposed child. | |
Trimethoprim (Monotrim) Hint: Trimethoprim is a folic acid antagonist, and should be avoided during organogenesis in the first trimester. | |
Nitrofurantoin (Macrobid) | |
Erythromycin (Ery-tab) Hint: Erythromycin is an ineffective treatment for asymptomatic bacteriuria. |
|
List |
References: Merck Manual · UpToDate