

 Lecture

Diverticulitis will present as → a 67-year-old man with a long history of constipation presents with steady left lower quadrant pain. Physical exam reveals low-grade fever, mid-abdominal distention, and lower left quadrant tenderness. Stool guaiac is negative. An absolute neutrophilic leukocytosis and a shift to the left are noted on the CBC.
Diverticulosis will present as → a 63-year-old male who is being evaluated in the emergency department for an episode of painless, bright red blood per rectum for two hours.

To watch this and all of Joe-Gilboy PA-C's video lessons you must be a member. Members can log in here or join now.
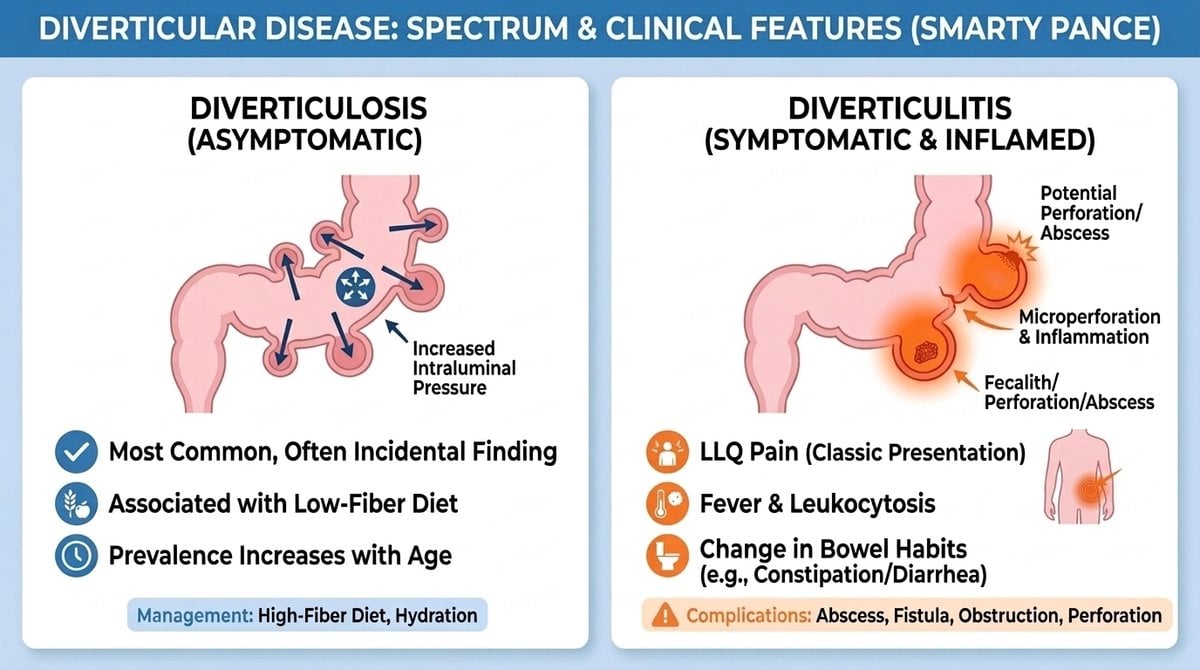
Diverticulosis = outpouchings of the mucosa and submucosa through weak spots in the colon wall where the blood vessels (vasa recta) enter; most common in the sigmoid colon
- Most people have no symptoms
- Risk factors: older age, low-fiber diet high in red meat, obesity, smoking, physical inactivity, NSAIDs
- Diverticular bleeding = sudden painless, large-volume hematochezia in an older adult (stretched vasa recta rupture); usually from the right colon and usually stops on its own

"Seeds and nuts — Contrary to popular opinion, nut, corn, and popcorn consumption are NOT associated with an increase in risk of diverticulosis, diverticulitis, or diverticular bleeding!"
Diverticulitis = inflammation of a diverticulum (a small perforation with surrounding inflammation), usually in the sigmoid colon
- LLQ pain, fever, ↑ WBC, ↑ CRP; change in bowel habits (constipation more often than diarrhea); bleeding is rare with diverticulitis
- Complicated diverticulitis = abscess, perforation, obstruction or stricture, or fistula (most often to the bladder → pneumaturia, fecaluria, recurrent UTIs)
A Dutch research group created a clinical prediction rule for acute diverticulitis that includes three indicators: The presence of all three indicators had a specificity of 98% and a positive predictive value of 97%
The presence of all three of the following indicators is considered a positive result
- Absence of vomiting
- C-reactive protein level > 5 mg per dL (50 mg per L)
- Tenderness is limited to the left lower quadrant
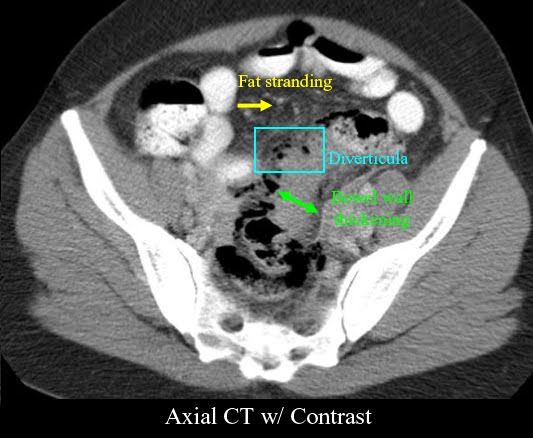
Diagnose with a CT of the abdomen and pelvis with IV contrast (oral contrast is optional); it also shows complications such as abscess, free air, fistula, or obstruction
- CT will demonstrate fat stranding and bowel wall thickening
- Occult blood in the stool and mild to moderate leukocytosis may occur with diverticulitis
- Upright chest or abdominal X-ray can show free air under the diaphragm (perforation) but is nonspecific; CT is preferred
- DO NOT perform a colonoscopy in an acute setting, as this can perforate the colon
- Colonoscopy 6–8 weeks after recovery if the episode was complicated, the CT or course was atypical, or the patient is not up to date on colorectal cancer screening (cancer can mimic diverticulitis)
- Diverticular bleeding: resuscitate → colonoscopy (finds and treats the source); unstable despite resuscitation → CT angiography → embolization; surgery is a last resort
The outpatient treatment of acute colonic diverticulitis typically consists of pain control and a liquid diet without antibiotics
- Clinicians may choose to use antibiotics for outpatients who may be at higher risk for poor outcomes (comorbidities, immunocompromised, or signs of systemic disturbance)
- Limit patients to a liquid diet until they can be reassessed in two to three days, after which their diet can be liberalized to soft or regular if they demonstrate clinical improvement

"Seeds, corn, and nuts – Patients with diverticular disease have historically been advised to avoid consuming seeds, corn, and nuts out of concern that undigested fragments of such food items could become lodged within a diverticulum and incite diverticulitis. However, this theory is completely unproven. Thus, we do not counsel patients with a history of diverticulitis against consuming seeds, corn, and nuts."
- Admit for complicated disease, sepsis, inability to take fluids, uncontrolled pain, age over 70 or significant comorbidity, or immunosuppression → IV antibiotics covering gram-negatives and anaerobes, IV fluids, bowel rest; nasogastric tube if ileus develops
- When antibiotics are used orally: amoxicillin-clavulanate, or ciprofloxacin (or TMP-SMX) plus metronidazole, usually for 4–7 days
- Abscess 3–4 cm or larger → CT-guided percutaneous drainage plus antibiotics; smaller abscesses → antibiotics alone
- Free perforation with generalized peritonitis → emergency surgery
- Elective sigmoid colectomy after complicated disease (fistula, stricture, obstruction) or persistent smoldering symptoms, not based on the number of uncomplicated attacks or young age
- Patients with diverticulosis should maintain a high-fiber diet to prevent diverticulitis. Evidence has negated the need to recommend the avoidance of nuts, seeds, and popcorn.
 Osmosis |
|
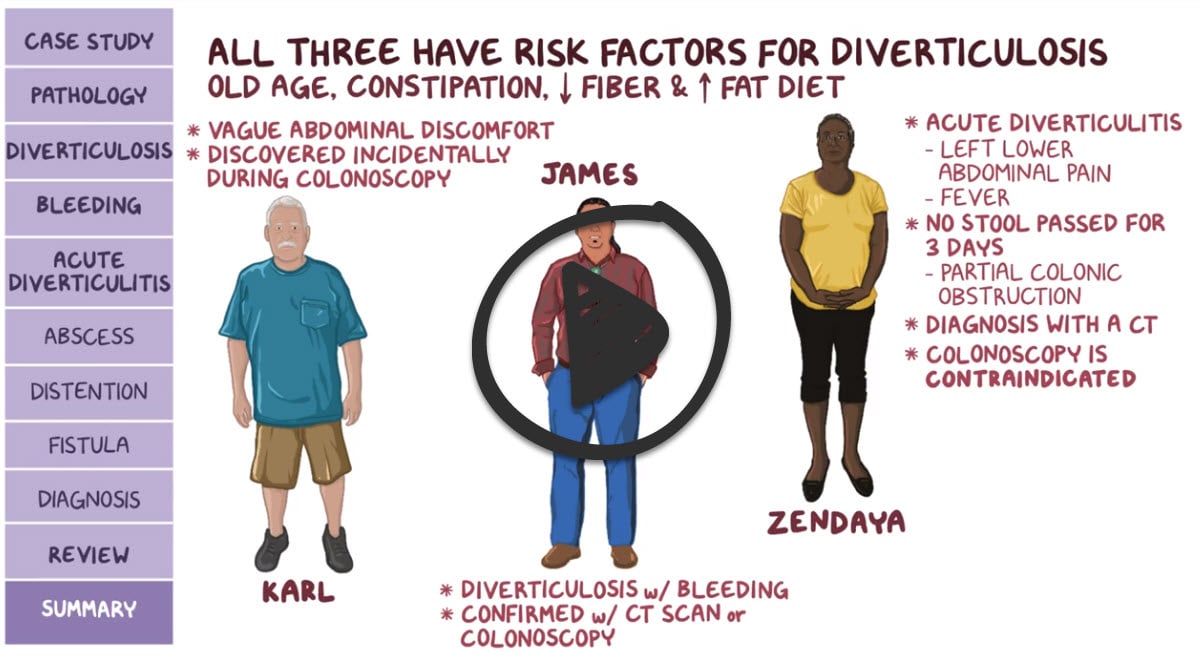 |

A patient with diverticula, outpouchings found in the descending, sigmoid colon, is said to have diverticulosis. Diverticula are common in the older adult and may never produce symptoms or complications. However, when the outpouchings become inflamed, the condition is called diverticulitis. If left untreated, diverticulitis can lead to perforation of the intestine and can cause peritonitis. Clinical manifestations of diverticulitis include lower left-side abdominal pain, abdominal distention, flatulence, fever, and constipation or diarrhea (rectal bleeding is uncommon with diverticulitis).
Play Video + QuizDiverticulosis and diverticulitis interventions
When a patient is diagnosed with diverticular disease, diet and lifestyle modifications must be made to prevent recurrence and/or exacerbations of the disease. Interventions include eating a diet high in fiber, taking products to soften the stool, reducing intra-abdominal pressure, and exercising. In severe instances, bowel resection may be necessary to remove the affected portion of the intestine.
Question 1 |
Eating nuts, corn, and popcorn Hint: Nuts, seeds, corn, and popcorn do NOT increase the risk of diverticulitis or diverticular bleeding; patients do not need to avoid them. | |
High-fiber diet Hint: A high-fiber diet is protective and is recommended for patients with diverticulosis. | |
Low-fiber diet high in red meat | |
Regular vigorous exercise Hint: Physical activity lowers the risk of diverticulitis and diverticular bleeding. | |
Statin therapy Hint: Statins are not a recognized risk factor for diverticulitis. |
Question 2 |
Barium enema Hint: Barium enema is avoided during an acute attack because of the risk of perforation and barium peritonitis. | |
Colonoscopy Hint: Colonoscopy is avoided during an acute attack because air insufflation can cause perforation; it is done 6 to 8 weeks after recovery when indicated. | |
CT of the abdomen and pelvis with IV contrast | |
Technetium-tagged red blood cell scan Hint: A tagged red blood cell scan localizes active GI bleeding; it does not diagnose diverticulitis. | |
Upright abdominal radiograph Hint: Plain films can show free air or obstruction but cannot confirm diverticulitis or show an abscess. |
Question 3 |
Admission for IV piperacillin-tazobactam Hint: She has no admission criteria (complicated disease, sepsis, inability to take fluids, uncontrolled pain, major comorbidity, or immunosuppression). | |
Clear liquid diet and oral analgesics with close follow-up | |
Elective sigmoid colectomy in 6 weeks Hint: Elective colectomy is offered after complicated diverticulitis, not after a first uncomplicated episode. | |
Oral ciprofloxacin and metronidazole for 14 days Hint: Antibiotics are used selectively in outpatients (major comorbidity, immunocompromise, or systemic illness); when used, courses are 4 to 7 days. | |
Urgent colonoscopy Hint: Colonoscopy is avoided during the acute attack because of perforation risk. |
Question 4 |
CT-guided percutaneous drainage | |
Emergency sigmoid colectomy with end colostomy Hint: Emergency surgery is reserved for free perforation with generalized peritonitis or failure of drainage and antibiotics. | |
Flexible sigmoidoscopy Hint: Endoscopy is avoided during acute diverticulitis because of perforation risk. | |
Oral antibiotics and discharge home Hint: A 5-cm abscess needs drainage and inpatient care; antibiotics alone are used for small abscesses (under about 3 to 4 cm). | |
Surgical incision and drainage through the perineum Hint: A pericolic abscess lies in the abdomen, not the perianal space, and is drained percutaneously under CT guidance. |
Question 5 |
Angiodysplasia Hint: Angiodysplasia also causes painless bleeding in older adults but is a less common cause of brisk lower GI bleeding. | |
Colorectal cancer Hint: Colorectal cancer usually causes slow occult bleeding, iron deficiency anemia, or a change in bowel habits rather than sudden large-volume bleeding. | |
Diverticular bleeding | |
Internal hemorrhoids Hint: Hemorrhoids cause small amounts of bright red blood on the toilet paper, not large-volume bleeding with tachycardia. | |
Ischemic colitis Hint: Ischemic colitis causes crampy abdominal pain followed by bloody diarrhea. |
Question 6 |
Daily mesalamine Hint: Mesalamine does not prevent recurrent diverticulitis and is not recommended. | |
Daily rifaximin Hint: Rifaximin is not recommended to prevent recurrent diverticulitis. | |
Elective sigmoid colectomy Hint: Elective colectomy is not based on the number of uncomplicated attacks or young age; it is offered after complicated disease or for persistent, smoldering symptoms. | |
High-fiber diet and observation | |
Low-residue diet that avoids nuts and seeds Hint: Nuts, seeds, corn, and popcorn do not increase risk, and a low-fiber diet is a risk factor. |
|
List |
References: Merck Manual · UpToDate