



85 y/o male with back pain, left-sided abdominal pain, and no bowel movements for 7 days
Patient will present as → a 65-year-old male with chronic low back pain complaining of bloating, abdominal pain, straining, and pain with bowel movements. He reports less than 3 bowel movements per week that are very hard and difficult to pass. The patient is on 50 mcg of transdermal Fentanyl and takes four 10 mg Norco per day for breakthrough pain.
Chronic (functional) constipation is infrequent, difficult, or incomplete defecation — defined by the Rome V criteria as ≥ 2 of the following for the last 3 months (symptom onset ≥ 6 months ago), each in ≥ 25% of defecations:
- Straining · lumpy/hard stools · incomplete evacuation · anorectal obstruction/blockage · manual maneuvers · < 3 spontaneous BMs/week
- Plus: loose stools rare without laxatives, and criteria for IBS not met (IBS-C = pain relieved/related to defecation)
- New-onset constipation at age 45 or older, or alarm features → evaluate for colon cancer
- Opioids are the classic drug cause — prophylax chronic opioid users with a scheduled stimulant laxative (senna) ± PEG — a stool softener alone is NOT enough
- Secondary causes — medications, DM, hypothyroidism, hypercalcemia, Parkinson's/MS, dehydration
Encopresis — recurrent stool soiling into clothing in a child > 4 years old, almost always overflow leakage around impacted stool from chronic withholding constipation
- Exam — distended abdomen, palpable LLQ mass, rectal vault full of stool; anal fissures or perianal irritation from soiling
- TX — disimpaction (oral PEG) → maintenance PEG for months + scheduled toilet sitting and behavioral training — do not punish soiling; it is involuntary
Clinical + rectal exam — hard stool, masses, fissures, hemorrhoids, sphincter tone and push effort, prostate in men, posterior vaginal masses in women
- Labs only if indicated — CBC, CMP (glucose, calcium), TSH for secondary causes; imaging rarely helpful in older adults
- ⚠️ New-onset constipation at age 45 or older, or any alarm feature (blood in stool, weight loss, iron-deficiency anemia, rectal pain, obstructive symptoms, FH of colon cancer or IBD) → colonoscopy
- Refractory → anorectal manometry + balloon expulsion (dyssynergic defecation → biofeedback) or colonic transit study
Increase fiber (20–35 g/day, increased gradually), fluids, and exercise — fiber's effect may take several weeks
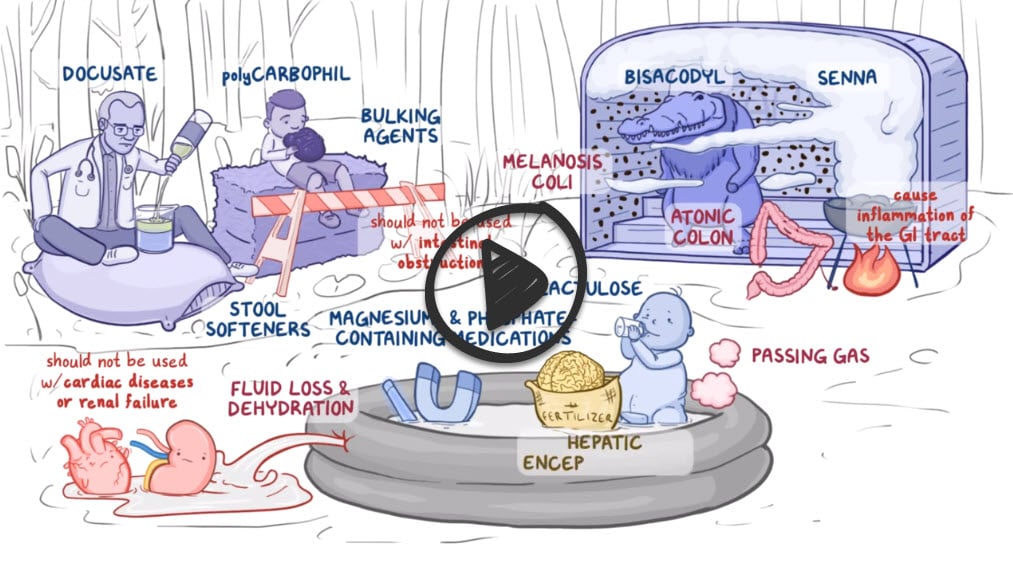
- Bulk-forming laxatives first-line — psyllium (Metamucil), methylcellulose (Citrucel), calcium polycarbophil, wheat dextrin
- Osmotic laxatives if fiber fails — start PEG 3350 (MiraLAX) 17 g daily, the preferred osmotic laxative (better than lactulose); effective and well tolerated in older adults

"FYI: Magnesium-based osmotic laxatives, such as magnesium citrate or magnesium hydroxide (Milk of Magnesia), may increase the risk of hypermagnesemia, especially in patients with CKD who are less able to excrete excess magnesium!"
- Stimulant laxatives (senna, bisacodyl) — enhance colonic motility; next step if osmotics fail, and first-line scheduled therapy for opioid-induced constipation (refractory OIC → PAMORA: methylnaltrexone, naloxegol)
- Docusate (stool softener) is not recommended (weak evidence); suppositories (glycerin/bisacodyl) and enemas for specific scenarios only — avoid sodium phosphate enemas in older adults and CKD
- Refractory constipation → investigate for the underlying cause (see Diagnosis) — linaclotide or plecanatide (or lubiprostone) for refractory chronic idiopathic constipation; prucalopride if these fail
 Osmosis |
|
 |
Question 1 |
Lisinopril Hint: ACE inhibitors do not typically slow the bowel; cough and hyperkalemia are their classic side effects. | |
Metformin Hint: Metformin more often causes diarrhea. | |
Metoprolol Hint: Beta-blockers rarely cause constipation. | |
Oxycodone | |
Sertraline Hint: SSRIs more often cause diarrhea or loose stools. |
Question 2 |
Chronic idiopathic constipation | |
Colonic pseudo-obstruction Hint: Acute colonic pseudo-obstruction (Ogilvie syndrome) is sudden massive colonic dilation, usually in hospitalized patients. | |
Hypothyroidism Hint: A normal TSH rules this out. | |
Irritable bowel syndrome with constipation Hint: IBS-C requires recurrent abdominal pain related to defecation; she has none. | |
Opioid-induced constipation Hint: She takes no medications. |
Question 3 |
Docusate sodium Hint: Stool softeners have weak evidence and are not recommended. | |
Linaclotide Hint: Secretagogues are used when osmotic and stimulant laxatives fail. | |
Polyethylene glycol 3350 | |
Prucalopride Hint: Prucalopride is used when secretagogues fail; it is not the first medication after fiber. | |
Sodium phosphate enema Hint: Not for routine use; phosphate enemas can cause electrolyte problems and kidney injury, especially in older adults and CKD. |
Question 4 |
Biofeedback therapy | |
Linaclotide Hint: More laxatives do not fix a pelvic floor coordination problem. | |
Prucalopride Hint: Prokinetics treat slow transit, not dyssynergia. | |
Sacral nerve stimulation Hint: Not a first-line treatment for dyssynergic defecation. | |
Subtotal colectomy Hint: Reserved for severe, refractory slow-transit constipation after defecatory disorders are excluded. |
Question 5 |
Cystic fibrosis Hint: Meconium ileus delays meconium, but it does not cause a tight, empty rectum with an explosive release of stool. | |
Functional constipation Hint: Functional constipation does not start at birth with delayed meconium, and the rectum is usually full of stool. | |
Hirschsprung disease | |
Hypothyroidism Hint: Congenital hypothyroidism causes constipation with prolonged jaundice, a large tongue, and hypotonia, and is found on newborn screening. | |
Infant botulism Hint: Infant botulism causes constipation with weakness, poor feeding, and hypotonia, usually at 1 to 6 months of age. |
Question 6 |
Initiate a trial of over-the-counter laxatives Hint: While these can be used to manage constipation, the patient's age and rectal bleeding warrant further investigation before initiating treatment. | |
Repeat colonoscopy | |
Abdominal X-ray Hint: This can identify fecal impaction but is less useful in excluding serious underlying pathology. | |
Prescribe a high-fiber diet and increased fluid intake Hint: Although beneficial in managing constipation, it's important to first rule out serious pathology in this patient. | |
Stool softeners and osmotic laxatives Hint: These are treatment options, but the patient first needs a thorough evaluation due to his age and symptoms. |
|
List |
References: Merck Manual · UpToDate