


Patient will present as → a 40-year-old woman who comes to your office with a several-year history of lower abdominal pain associated with constipation (one hard bowel movement every 3 days) and frequent mucus discharge. She states that her abdominal pain is better after a bowel movement. She has never passed blood per rectum. She describes no fever, chills, weight loss or gain, jaundice, or any other symptoms. There is no relationship between the abdominal pain and specific food intake. On physical examination, the abdomen is scaphoid, and no hepatosplenomegaly or masses are palpated. There is a mild generalized abdominal tenderness, but it does not localize.
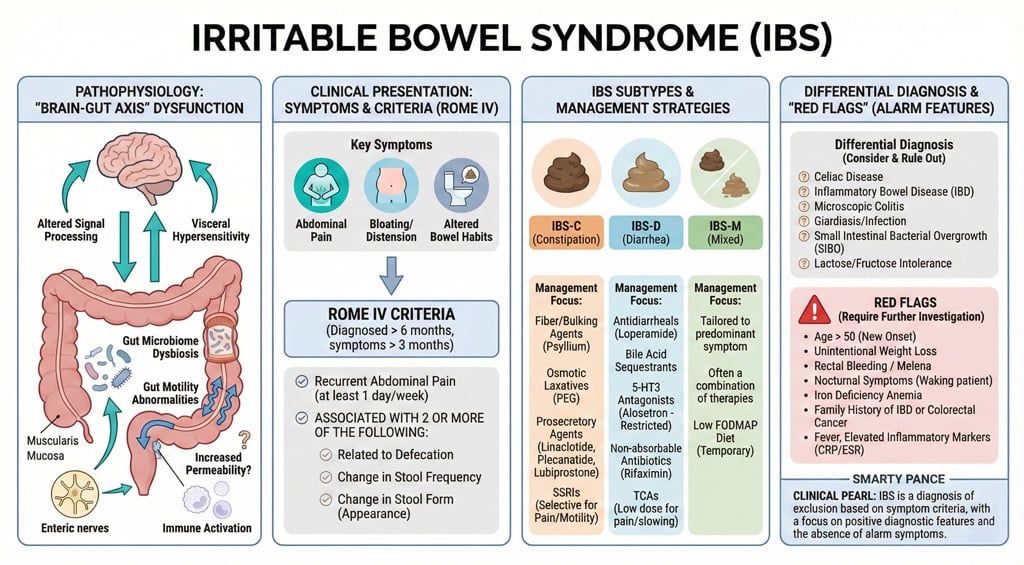
Irritable bowel syndrome is a chronic disorder of gut–brain interaction (a functional gastrointestinal disorder) characterized by recurrent abdominal pain associated with altered bowel habits, made as a positive clinical diagnosis using the Rome criteria when there are no alarm features and limited testing is normal — it is not a diagnosis of exclusion.
IBS subtypes are based on the predominant stool form on days with abnormal bowel movements (Bristol Stool Form Scale):
- IBS with predominant constipation (IBS-C): more than 25% of bowel movements are hard or lumpy (Bristol types 1–2)
- IBS with predominant diarrhea (IBS-D): more than 25% of bowel movements are loose or watery (Bristol types 6–7)
- Mixed IBS (IBS-M): more than 25% hard or lumpy and more than 25% loose or watery
- Unclassified IBS (IBS-U): Patients who meet diagnostic criteria for IBS but cannot be accurately categorized into one of the other three subtypes
IBS is a disorder of gut–brain interaction: altered gut motility, visceral hypersensitivity, changes after an episode of gastroenteritis (post-infectious IBS), shifts in the gut microbiome, and stress all contribute
- Bloating, gas, and mucus in the stool are common
- Pain is related to defecation (usually eased, sometimes worsened, by a bowel movement)
- Bowel movements are irregular and vary from constipation to diarrhea
- Related to defecation (pain improves or worsens with a bowel movement)
- Associated with a change in stool frequency
- Associated with a change in stool form (appearance)
Continuous, all-day pain does not fit IBS → think centrally mediated abdominal pain syndrome.
Board tip: Older Rome IV wording (still in many review books and practice questions) required pain only, at least 1 day per week. Either way, the pattern is the same: chronic abdominal pain tied to bowel movements, plus a change in stool frequency or form, with no alarm features.
The diagnosis of IBS can reasonably be made using the Rome criteria as long as patients have no red flag (alarm) findings, such as symptom onset at age 45 or older, rectal bleeding, nocturnal diarrhea, progressive pain, unexplained weight loss, iron deficiency anemia, elevated inflammatory markers, or a family history of inflammatory bowel disease (IBD), colorectal cancer, or celiac disease. IBS is a positive diagnosis, not a diagnosis of exclusion.
- Patients with a red flag finding need further evaluation, usually colonoscopy
- Testing is limited: Complete blood count (CBC) and age-appropriate colorectal cancer screening for everyone; with diarrhea, add fecal calprotectin (or lactoferrin), a Giardia stool test, and celiac serology (tissue transglutaminase IgA). Results are normal in IBS
Treat the dominant symptom. Start with education, reassurance, and diet, then add medication.
- Everyone: regular exercise and stress management, soluble fiber (psyllium) — not insoluble fiber like wheat bran, which worsens bloating — and a time-limited low-FODMAP diet trial with planned food reintroduction
- Pain and cramping: peppermint oil, antispasmodics (dicyclomine, hyoscyamine), or a low-dose tricyclic antidepressant (nortriptyline, amitriptyline); gut-directed psychotherapy (cognitive behavioral therapy, hypnotherapy) also helps
- IBS-C: polyethylene glycol (PEG) eases constipation but not pain → secretagogues: linaclotide or plecanatide (guanylate cyclase-C agonists), lubiprostone (chloride-channel activator), or tenapanor
- IBS-D: loperamide (firms stools but does not help pain), rifaximin (nonabsorbable antibiotic for bloating and global symptoms), eluxadoline (avoid after cholecystectomy, with heavy alcohol use, or with prior pancreatitis), and alosetron (only for women with severe, refractory IBS-D — risk of ischemic colitis)
- Not recommended: probiotics (inconsistent benefit), SSRIs as primary therapy (use only for coexisting anxiety or depression), and tegaserod (withdrawn from the US market)
 Osmosis |
|
 |

Irritable bowel syndrome (IBS) is characterized as a chronic gastrointestinal disorder that includes symptoms of abdominal pain, alterations in bowel patterns, excessive flatulence, and fatigue. However, these symptoms are widely individualized, which makes IBS difficult to diagnose. Symptoms may be exacerbated by psychosocial stressors and certain foods. This condition is more commonly diagnosed in women. Although there is no specific test to identify IBS, diagnostic tests for other health conditions are performed to rule them out.
Play Video + QuizIrritable Bowel Syndrome (IBS) Interventions

The goal of IBS treatment includes decreasing symptoms by increasing dietary fiber and administering medications such as anticholinergics, loperamide, tricyclic antidepressants, and linaclotide. Medications specific to women include lubiprostone and alosetron (tegaserod has since been withdrawn from the US market). Identifying and reducing risk factors that exacerbate IBS is critical to help avoid exacerbations of the condition.
Question 1 |
Steroid enemas Hint: See C for explanation | |
Mesalamine enemas Hint: See C for explanation | |
Peppermint oil | |
Metoclopramide Hint: See C for explanation | |
None of the above |
Question 2 |
It is a diagnosis of exclusion Hint: See B for explanation | |
It is an organic disorder | |
Young women are affected 2–3 times more often than men Hint: See B for explanation | |
May occur following an episode of gastroenteritis Hint: See B for explanation |
Question 3 |
Irritable bowel syndrome | |
Lactase deficiency Hint: Presents as diarrhea and flatulence following ingestion of milk. | |
Ulcerative colitis Hint: Presents as bloody diarrhea | |
Crohn disease Hint: Physical examination would reveal a mass at the right lower quadrant. |
Question 4 |
Colonoscopy Hint: See D for explanation | |
Barium enema Hint: See D for explanation | |
Abdominal radiograph Hint: See D for explanation | |
None of the above |
Question 5 |
Alvarado score Hint: Is used in making a diagnosis of acute appendicitis. | |
Ranson criteria Hint: Is used in assessing the severity of acute pancreatitis. | |
Rome criteria | |
Revised Jones criteria Hint: Is used in diagnosing rheumatic fever. |
Question 6 |
Giardia lamblia | |
Escherichia coli | |
Shigella | |
Salmonella |
Question 7 |
Painless diarrhea | |
Fever | |
Postprandial urgency | |
Steatorrhea |
Question 8 |
Altered stool frequency | |
Mucorrhea | |
Abdominal bloating or subjective distention | |
Frequent nausea |
Question 9 |
Iron deficiency anemia | |
Abdominal pain | |
Amenorrhea | |
Hypokalemia |
|
List |
References: Merck Manual · UpToDate