

 Lecture

51-year-old with rectal bleeding and abdominal pain
Patient will present as → a 45-year-old man with severe rectal pain when he defecates, which lasts for several hours and subsides until the next bowel movement. He has been constipated for the past 6 months, and when he does have a bowel movement, the stool is covered with bright red blood. A sentinel pile is noted on the physical exam.

To watch this and all of Joe-Gilboy PA-C's video lessons, you must be a member. Members can log in here or join now.
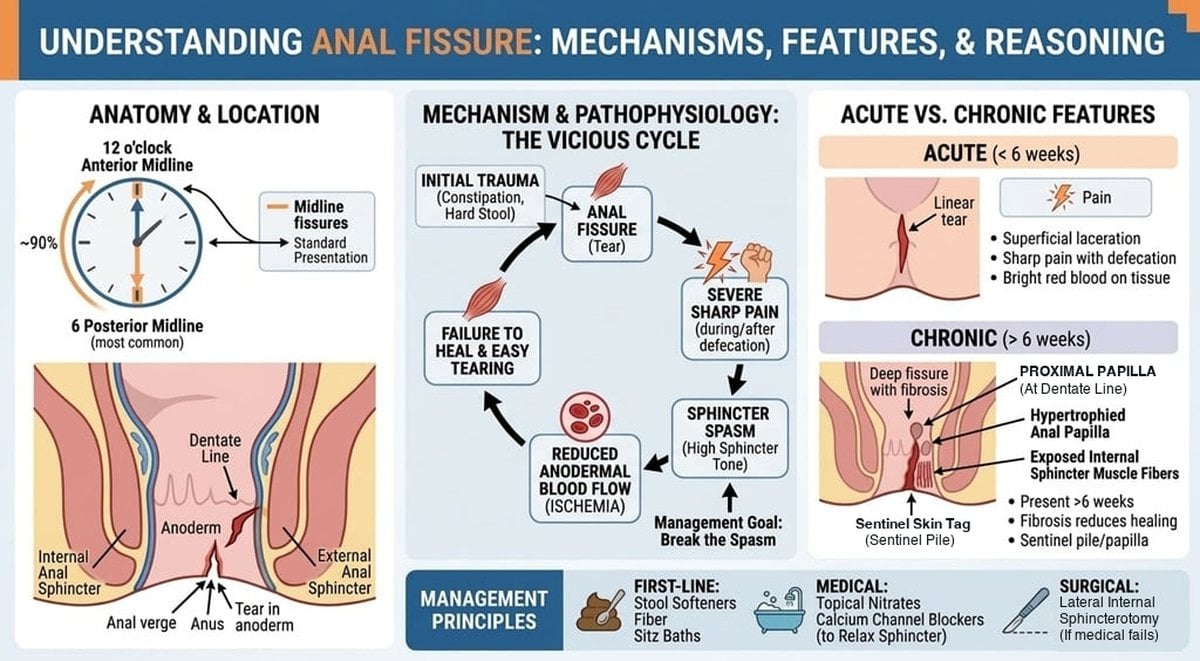
Anal fissures are believed to result from laceration by a hard or large stool or from frequent loose bowel movements
- Posterior midline in about 90% (the least well-perfused part of the anal canal); anterior midline fissures are more common in women
- Caused by: hard stool passage (constipation), hyperactive sphincter, disease process (e.g., Crohn’s disease)
- The fissure may cause internal sphincter spasm (high resting tone → ischemia), decreasing blood supply and perpetuating the fissure
- Presents with pain in the anus, painful (can be excruciating) bowel movement that lasts for hours, rectal bleeding, blood on toilet tissue after bowel movement, sentinel tag, tear in the anal skin, extremely painful rectal exam, sentinel pile, hypertrophic papilla

An anal fissure is a small tear in the thin, moist tissue (mucosa) that lines the anus. 90% of fissures are formed along the posterior midline of anal canal.
Diagnosis is made by history and visual inspection with gentle separation of the buttocks
- Avoid a digital rectal exam or anoscopy at the first visit (they cause severe pain); do them at follow-up once the pain settles
- A sentinel pile (thickened mucosa) is found below the fissure
- Unless findings suggest a specific cause or the appearance and/or location is unusual, further studies are not required
- Atypical fissure (lateral, multiple, painless, deep, or nonhealing) → work up for Crohn disease, tuberculosis, HIV, syphilis, or anal cancer
For patients with a typical anal fissure (ie, a single posterior or anterior fissure with no evidence of Crohn's disease), treatment consists of a combination of supportive measures (fiber, sitz bath, topical analgesic) and one of the topical vasodilators (nifedipine or nitroglycerin) for one month.
Treatment acronym WASH
- W arm sitz baths: which can relax the anal sphincter and improve blood flow to the anal mucosa, are recommended for patients with anal fissures
- During a sitz bath, the anus is immersed in warm water for approximately 10 to 15 minutes two to three times daily or showers immediately after every bowel movement
- A nalgesics: 2% lidocaine jelly
- Topical vasodilator:
- topical 0.4% nitroglycerin rectal ointment (Rectiv) twice daily
- topical 0.2 to 0.3% nifedipine ointment two to four times daily in patients who have access to a compounding pharmacy
- Topical vasodilator:
- S tool softeners (Colace)
- H igh Fiber: the recommended dietary fiber intake is between 20 and 35 grams per day
- Patients who continue to have difficulty with hard bowel movements despite increasing dietary fiber intake may use fiber supplements, such as psyllium seed (Metamucil), methylcellulose (Citrucel), wheat dextrin (Benefiber), and calcium polycarbophil (Fibercon)
Refractory fissure (not healed after about 8 weeks of medical therapy)
- Topical diltiazem 2% gel is an alternative vasodilator when nifedipine is not available or nitroglycerin is not tolerated (headache, low blood pressure; no PDE-5 inhibitor within 24 hours of nitroglycerin)
- Lateral internal sphincterotomy is the most effective treatment (gold standard) for chronic fissures that fail medical therapy, in patients without risk factors for incontinence
- Botulinum toxin type A injection (or fissurectomy or an advancement flap) if there are incontinence risk factors: prior anorectal surgery, obstetric sphincter injury, inflammatory bowel disease, or chronic loose stools
- Endoscopy before surgery to exclude Crohn disease
Question 1 |
Engorgement of the internal hemorrhoidal plexus Hint: Hemorrhoids cause painless bleeding; engorged cushions do not cause a nonhealing midline tear. | |
Granulomatous transmural inflammation Hint: Crohn disease causes atypical fissures (lateral, multiple, often painless), not a typical posterior midline tear after constipation. | |
High internal anal sphincter tone with local ischemia | |
Infection of an obstructed anal crypt gland Hint: Crypt gland infection causes an anorectal abscess or fistula, with constant pain and a tender mass. | |
Squamous dysplasia of the anoderm Hint: Anal cancer can cause an atypical, nonhealing fissure; this is a typical posterior fissure after constipation. |
Question 2 |
Anoscopy Hint: Anoscopy is very painful with an acute fissure; save it for follow-up once the pain settles. | |
Colonoscopy Hint: Not needed to diagnose a typical fissure; consider endoscopy later for atypical or nonhealing fissures, alarm features, or age-based screening. | |
Digital rectal examination Hint: A digital exam causes severe pain and spasm; defer it until symptoms improve. | |
Magnetic resonance imaging of the pelvis Hint: MRI is used to map complex fistulas, not to diagnose a fissure. | |
Visual inspection with gentle separation of the buttocks |
Question 3 |
Botulinum toxin injection Hint: Botulinum toxin is a second-line option after topical therapy fails, or when incontinence risk makes surgery unwise. | |
Fiber supplement, sitz baths, and topical nifedipine | |
Lateral internal sphincterotomy Hint: Sphincterotomy is for fissures that fail about 8 weeks of medical therapy (or long-standing chronic fissures). | |
Oral metronidazole Hint: A fissure is not an infection; antibiotics have no role. | |
Rubber band ligation Hint: Banding treats internal hemorrhoids, not fissures. |
Question 4 |
Excisional hemorrhoidectomy Hint: Hemorrhoidectomy treats advanced hemorrhoids, not a fissure. | |
Fistulotomy Hint: Fistulotomy lays open a fistula tract; she has no fistula. | |
Lateral internal sphincterotomy | |
Rubber band ligation Hint: Banding treats internal hemorrhoids, not a fissure. | |
Topical hydrocortisone Hint: Steroids do not relax the sphincter or heal a fissure. |
Question 5 |
Crohn disease | |
Hemorrhoidal disease Hint: Hemorrhoids cause painless bleeding or prolapse, not multiple lateral fissures. | |
Irritable bowel syndrome Hint: IBS does not cause weight loss or atypical fissures. | |
Pilonidal disease Hint: Pilonidal disease sits in the natal cleft, away from the anus. | |
Proctalgia fugax Hint: Proctalgia fugax is brief, severe rectal pain with a normal exam. |
|
List |
References: Merck Manual · UpToDate