

 Lecture

Patient with a rectal abscess will present as → a 45-year-old man presents to the emergency department with a 3-day history of constant, throbbing rectal pain that is worse when sitting and with bowel movements. He also reports fever and malaise. On physical examination, you note a fluctuant, erythematous mass near the anus. The patient is in obvious discomfort.
Patient with an anorectal fistula will present as → a 45-year-old man presents to the clinic with a 3-month history of recurrent perianal abscesses. He reports intermittent drainage of pus and discomfort in the perianal area. On examination, you note a small opening near the anal verge with surrounding erythema. A probe is easily passed through the opening and emerges in the anal canal.

To watch this and all of Joe-Gilboy PA-C's video lessons you must be a member. Members can log in here or join now.
An anorectal abscess is a collection of pus in the area around the anus and rectum and is the result of infection, whereas an anorectal fistula is an abnormal tunnel that connects the anus or rectum to the skin around the anus and is a chronic complication of an abscess.
- Most begin as an infected anal crypt gland (cryptoglandular) at the dentate line; perianal abscess is the most common type
- Abscesses produce constant, painful swelling at the anus as well as painful defecation. Examination reveals localized tenderness, erythema, swelling, and fluctuance; fever is uncommon.
- Deeper abscesses may produce buttock or coccyx pain and rectal fullness; fever is more likely.
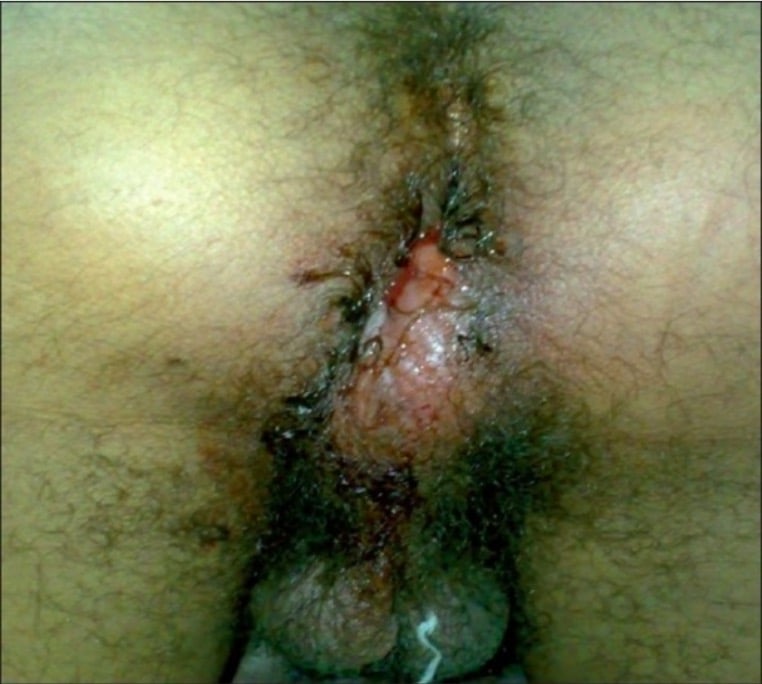
Perianal swelling, erythema, and drainage due to a perianal abscess by the Department of Urology, University Hospital Center, Fez, Morocco. Image - License: CC BY 2.0
An anorectal fistula is an open tract between two epithelium-lined areas and is associated with deeper anorectal abscesses
- Communication between the rectum and perianal skin
- Generally located within 3 cm of the anal margin
- More than 90% are cryptoglandular (follow an abscess, in about a third of patients after drainage); Crohn disease is the key secondary cause — think of it with multiple, recurrent, or complex fistulas
- Goodsall rule: an external opening posterior to a line across the anus tracks in a curve to the posterior midline; an anterior opening runs straight (radially) into the canal
- Fistulae will produce anal discharge and pain when the tract becomes occluded
Intraoperative view of the external openings of the fistula in ano (arrowheads) and the upper part of the tract where the foreign material resided (arrow)
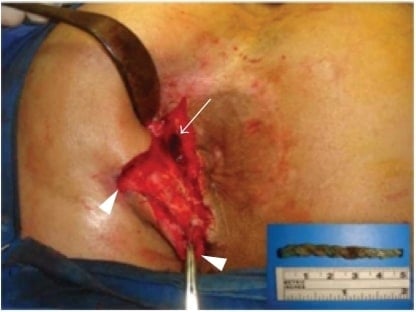
Intraoperative view of the external openings of the fistula in ano (arrowheads) and the upper part of the tract where the foreign material resided (arrow) by Department of General Surgery, Cerrahpasa Medical School, Istanbul University, Cerrahpasa, Fatih 34098, Istanbul, Turkey. Image - License: CC BY 3.0
Anorectal fistulas and abscesses are typically diagnosed through a physical examination and medical history
Anal Abscess - Clinical - perirectal tender swollen mass
- CT or MRI of the pelvis (or endoanal ultrasound) only when a deep abscess is suspected but cannot be seen or felt
Fistula in Ano (perianal fistula)
- Clinical: external opening ± palpable cord-like tract; confirmed by probing the tract during an exam under anesthesia
- MRI of the pelvis (or endoanal ultrasound) for complex, recurrent, or Crohn-related fistulas
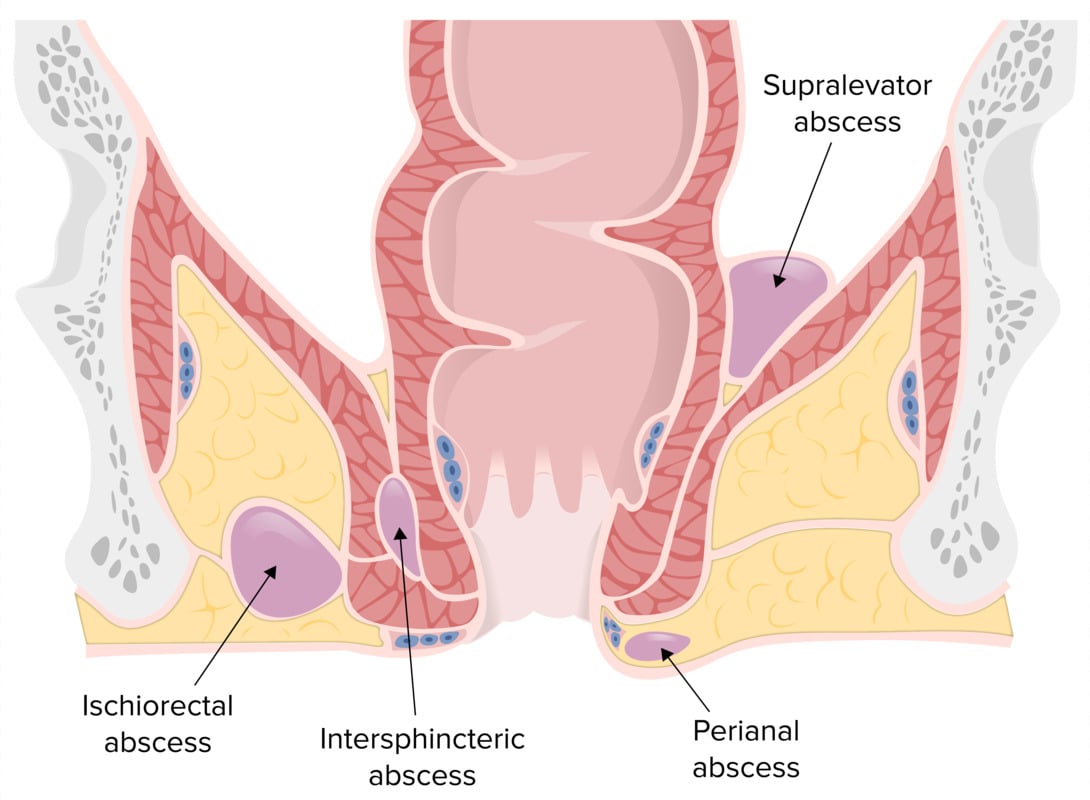
Treatment of an anorectal abscess requires prompt incision and drainage, followed by warm-water cleansing, analgesics, stool softeners, and a high-fiber diet are prescribed for all patients
- Prompt incision and adequate drainage are required and should not wait until the abscess points. Many abscesses can be drained as an in-office procedure; deeper abscesses may require drainage in the operating room
- Antibiotics after drainage for extensive cellulitis, systemic signs or sepsis, diabetes, immunosuppression, or valvular heart disease
- Packing the cavity is usually not needed
Anorectal fistulas must be treated surgically (antibiotics do not cure them)
- Simple fistula (low, little sphincter involved) with normal continence → fistulotomy
- Complex fistula (high, much sphincter involved, multiple, Crohn-related, or existing incontinence) → draining seton first, then a sphincter-sparing repair (LIFT or advancement flap)

A fistula is a connection or passageway formed abnormally between two epithelium-lined vessels or organs. Causes of enterocutaneous fistulas can be summarized by the mnemonic “FRIEND.” The “FRIENDs” of a fistula include Foreign body, Radiation, Infection, Epithelialization, Neoplasm, and Distal obstruction.
Play Video + QuizQuestion 1 |
Chronic infection of an obstructed anal crypt gland | |
Ischemia of the posterior midline anoderm Hint: Posterior midline ischemia explains a nonhealing anal fissure, not a draining tract. | |
Prolapse of the internal hemorrhoidal cushions Hint: Prolapsing hemorrhoids cause painless bleeding and a reducible bulge, not a draining opening. | |
Thrombosis of an external hemorrhoidal vein Hint: A thrombosed external hemorrhoid is an acutely painful bluish lump at the anal verge. | |
Transmural granulomatous bowel inflammation Hint: Crohn disease is the key secondary cause; suspect it with multiple, recurrent, or complex fistulas or bowel symptoms, which he does not have. |
Question 2 |
Anoscopy Hint: Anoscopy may show an internal opening but cannot map deep or branching tracts. | |
Barium enema Hint: A barium enema shows the colon lumen, not perianal tracts. | |
Computed tomography of the pelvis Hint: CT helps find a deep abscess but maps fistula tracts less accurately than MRI. | |
Fistulography Hint: Fistulography is uncomfortable and less accurate than MRI; it is rarely used now. | |
Magnetic resonance imaging of the pelvis |
Question 3 |
Computed tomography of the pelvis Hint: Imaging is for a suspected deep abscess that cannot be felt; this one is obvious on exam. | |
High-fiber diet and sitz baths Hint: Supportive care helps after drainage but does not treat the abscess. | |
Incision and drainage | |
Oral antibiotics alone Hint: Antibiotics cannot replace drainage of a pus collection. | |
Topical nitroglycerin Hint: Nitroglycerin ointment treats anal fissures. |
Question 4 |
Fistulotomy | |
Long-term oral antibiotics Hint: Antibiotics do not close an established fistula tract. | |
Rubber band ligation Hint: Banding treats internal hemorrhoids. | |
Systemic corticosteroids Hint: Steroids do not treat cryptoglandular fistulas. | |
Topical diltiazem Hint: Topical diltiazem treats anal fissures. |
Question 5 |
Antibiotic therapy | |
Daily wound packing Hint: Packing after drainage adds pain without improving healing and is not routinely needed. | |
Fistulotomy Hint: No fistula has been found; a fistula is treated electively if one develops. | |
Routine wound culture Hint: Cultures are not routine; consider them for recurrent abscesses, immunosuppression, or suspected MRSA. | |
Topical nifedipine Hint: Nifedipine ointment treats anal fissures. |
|
List |
References: Merck Manual · UpToDate