



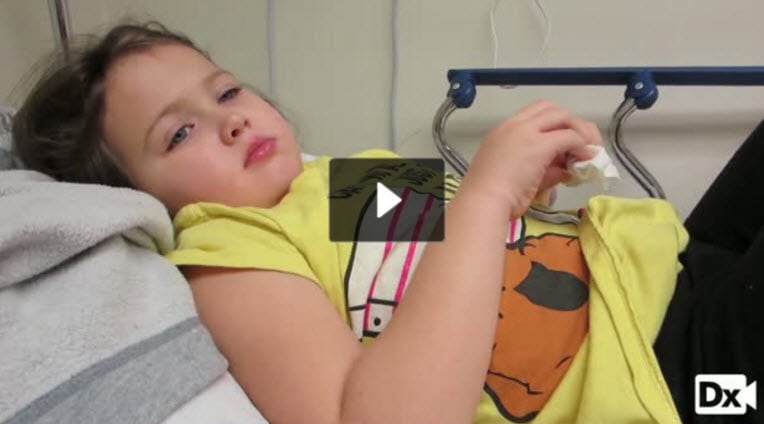
5 y/o with fever and emesis
Patient will present as → a 5-year-old with sudden onset of fever, chills, malaise, sore throat, headache, and coryza. The child is also complaining of myalgia, especially in her back and legs. On physical exam, the patient appears lethargic, has a temperature of 102.5 F, and palpable cervical lymph nodes. Breath sounds are distant with faint end-expiratory wheezes. CXR demonstrates bilateral diffuse infiltrates.
Influenza is a viral respiratory infection caused by orthomyxovirus, resulting in fever, coryza, cough, headache, and malaise - three strains exist: A, B, and C
- Patients will present with fever, headache, myalgia, and malaise
- Complications from influenza are most common in the very young, the very old, and those with preexisting comorbidities
- Avoid vaccination if:
- Prior severe reaction to flu vaccine (consult allergist)
- <6 months old
- Avoid FluMist if asthma or chronic lung conditions
- Note: Egg allergy (any severity) is not a contraindication; no special precautions are needed. However, providers must be prepared for rare anaphylaxis
Antivirals are most effective if administered within the first 48 hours and reduce the duration of illness by about one day
- Four antiviral medications approved by the U.S. FDA are recommended
- Inhaled Zanamivir (Relenza), oral Oseltamivir (Tamiflu), and intravenous peramivir (Rapivab) are all neuraminidase inhibitors and treat influenza A and B
- The fourth drug, which is oral baloxavir (Xofluza), is active against both influenza A and B viruses and is a cap-dependent endonuclease inhibitor that interferes with viral RNA transcription and blocks virus replication
- Amantadine and Rimantadine are in a class of medications known as adamantanes, which target the M2 ion channel protein of influenza A viruses
Diagnosis is based primarily on patient history. A rapid antigen test can be performed in the clinic - the virus can be isolated from the throat or nasal mucosa
- Rapid molecular assays (nucleic acid amplification tests) are preferred over rapid antigen tests because they are far more sensitive and return results within minutes to hours
- Gold standard = RT-PCR (molecular testing); viral culture takes 3 to 7 days and is used mainly for public health surveillance
- CXR in primary influenza pneumonia will show bilateral diffuse infiltrates
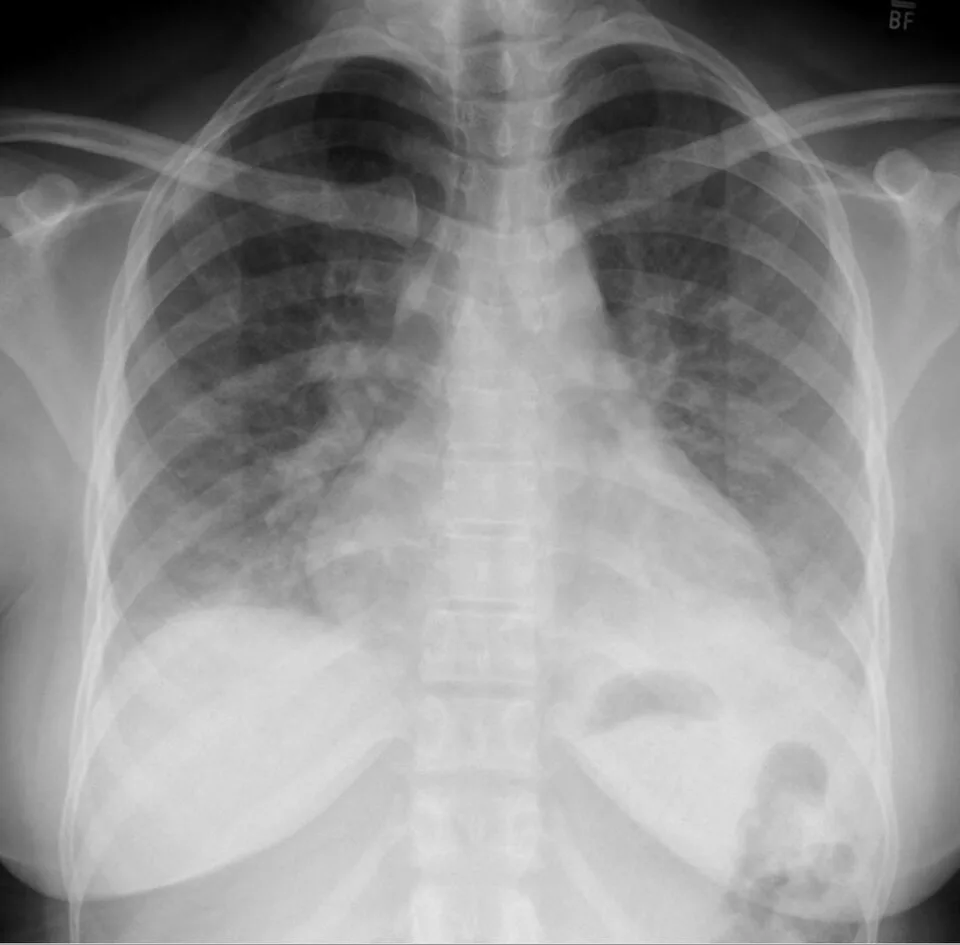
Chest radiograph from a patient with viral pneumonia showing widespread bilateral interstitial infiltrates. Image: Hellerhoff, CC BY-SA 4.0, via Wikimedia Commons.
Who to treat: start an antiviral as soon as possible, without waiting for test results, in any patient who is hospitalized, has severe, complicated, or progressive illness, or is at higher risk for complications (age ≥ 65, children < 5 and especially < 2, pregnancy and up to 2 weeks postpartum, chronic lung/heart/kidney/liver/metabolic disease, immunosuppression, body mass index ≥ 40, long-term care residents). In these groups, treat even if symptoms have been present for more than 48 hours. For otherwise healthy outpatients, antivirals are optional and only help if started within the first 48 hours of symptom onset (they shorten illness by about one day).
Four antiviral medications approved by the U.S. Food and Drug Administration (FDA) are recommended by the CDC. All four are active against both influenza A and B.
- Three are neuraminidase inhibitors that block release of new virus from infected cells:
- Oral oseltamivir (Tamiflu) – twice daily for 5 days; approved for any age. Drug of choice for hospitalized patients and in pregnancy. Post-exposure prophylaxis: once daily for 7 days, started within 48 hours of exposure
- Inhaled zanamivir (Relenza) – 2 inhalations twice daily for 5 days; age ≥ 7 years. Avoid in asthma or COPD (risk of bronchospasm)
- Intravenous peramivir (Rapivab) – single IV dose; age ≥ 6 months; for patients who cannot take oral or inhaled medication
- The fourth is a cap-dependent endonuclease inhibitor that interferes with viral RNA transcription and blocks virus replication:
- Oral baloxavir (Xofluza) – single weight-based oral dose; age ≥ 5 years; for uncomplicated influenza in outpatients. Not recommended in pregnancy, breastfeeding, hospitalized patients, or the severely immunocompromised
*** Zanamivir and Oseltamivir both treat influenza A and B (think Dr. “OZ” treats the flu)
Amantadine and rimantadine are adamantanes that block the M2 ion channel of influenza A only. They are no longer recommended for treatment or prophylaxis because circulating influenza A strains are almost universally resistant.
Supportive care is the mainstay for healthy outpatients: rest, fluids, and acetaminophen or ibuprofen for fever and myalgias. Salicylates should be avoided in anyone under 18 because of the association with Reye syndrome - remember that bismuth subsalicylate (Pepto-Bismol) contains salicylate too.
Responsible use of antivirals:
- Do not delay treatment while waiting for testing - a negative rapid antigen test does not rule out influenza in a hospitalized or high-risk patient
- Antivirals are recommended for every hospitalized patient and for every high-risk outpatient (e.g., diabetes, coronary heart disease, COPD, asthma, pregnancy, age ≥ 65), regardless of illness duration
- Antivirals may be offered to healthy, low-risk outpatients whose symptoms began within the past 48 hours and who wish to shorten their illness; otherwise symptomatic treatment alone is appropriate
- Post-exposure chemoprophylaxis (oseltamivir, zanamivir, or baloxavir) can be considered for high-risk close contacts when started within 48 hours of exposure - it is not a substitute for vaccination
- Antiviral resistance patterns can shift from season to season; check www.cdc.gov/flu or the local health department for current guidance
CDC guidelines for influenza outbreak management in long-term care facilities and post-acute care facilities
When at least 2 patients are ill within 72 hours of each other and at least one resident has laboratory-confirmed influenza, the facility should promptly initiate antiviral chemoprophylaxis with oral oseltamivir to all non-ill residents living on the same unit as the resident with laboratory-confirmed influenza (outbreak affected units), regardless of whether they received influenza vaccination during the current season.
- Consideration may be given for extending antiviral chemoprophylaxis to residents on other unaffected units or wards in the long-term care facility based upon other factors (e.g. unavoidable mixing of residents or staff from affected units and unaffected units).
Influenza Antiviral Medications at a Glance (per CDC) – all four cover influenza A and B
| Antiviral | Treatment | Chemoprophylaxis | Cautions and adverse effects |
| Oral oseltamivir (Tamiflu) | Any age; twice daily × 5 days | ≥ 3 months; once daily × 7 days | Preferred in pregnancy and for hospitalized patients. Nausea, vomiting, headache |
| Inhaled zanamivir (Relenza) | ≥ 7 years; twice daily × 5 days | ≥ 5 years; once daily × 7 days | Avoid in asthma or COPD (bronchospasm); sinusitis, dizziness |
| IV peramivir (Rapivab) | ≥ 6 months; single IV dose | Not recommended | For patients who cannot take oral therapy. Diarrhea; rare serious skin reactions |
| Oral baloxavir (Xofluza) | ≥ 5 years; single weight-based dose | ≥ 5 years; single dose | Not for pregnancy, breastfeeding, hospitalized, or severely immunocompromised patients. Separate from dairy, calcium, and antacids (reduced absorption) |
Adamantanes (amantadine, rimantadine) are not recommended – circulating influenza A viruses are resistant.
 Osmosis |
|
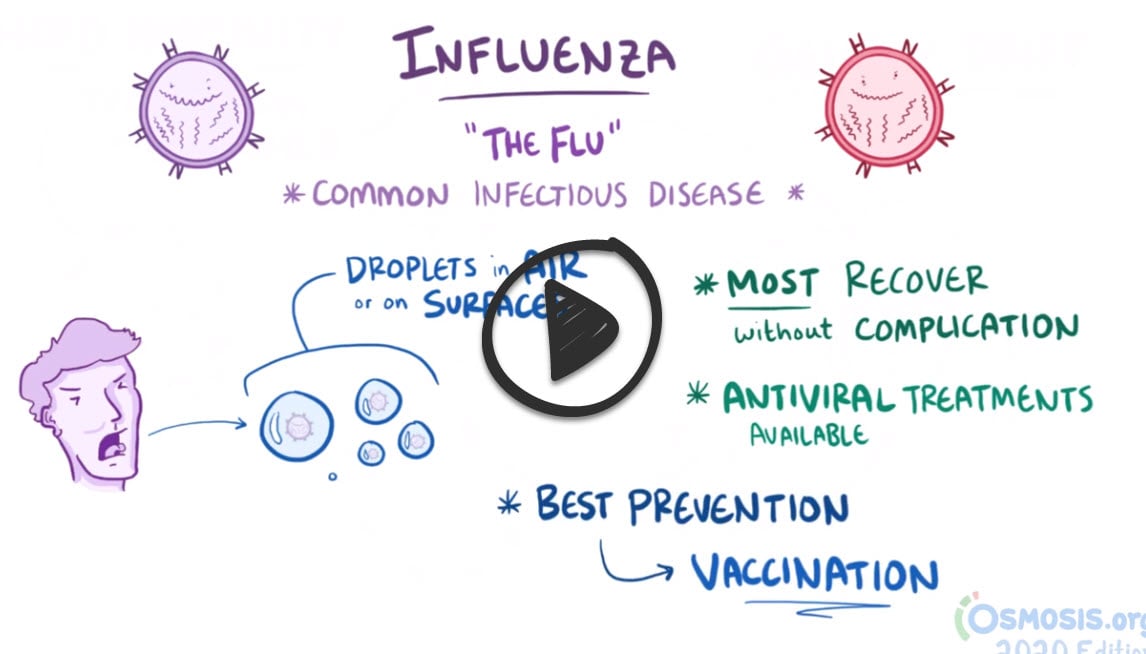 |
Influenza, commonly called the flu, is an infectious disease caused by an RNA virus of the Orthomyxovirus family. This is an enveloped virus with single-stranded negative sense linear genome. The genome is also segmented into 8 segments and has helical protein capsid. Virulence mechanisms include hemagglutinin, which is an antigenic glycoprotein found on the surface of influenza viruses that aids in viral entry of a cell and neuraminidase, an enzyme that plays an important role in the release of virion progeny from infected cells. This virus has the capacity to undergo reassortment of the genome to cause major changes in the strain of influenza. This major change is commonly referred to as genetic shift and can be highly dangerous because the human immune system has difficulty recognizing the new strain of the virus. In contrast, genetic drift refers to minor antigenic mutations that occur and are associated with gradual loss of immunity. Common symptoms of influenza virus include chills, fever, sore throat, muscle pains, headache, and fatigue. Complications include Reye’s syndrome, a potentially fatal disease commonly associated with salicylate use in children with influenza, and the virus can also be a trigger for Guillain-Barré syndrome.
Play Video + QuizZanamivir (Relenza) and Oseltamivir (Tamiflu)

Zanamivir (Relenza) and Oseltamivir (Tamiflu) are antiviral medications used to treat and provide prophylaxis against influenza A and B. These drugs work by binding to neuraminidase, preventing the virus from escaping its host cell and infecting others.
Reye’s syndrome

Reye’s syndrome is a disorder associated with salicylate use in children with viral illnesses, such as the chickenpox and influenza. For this reason, aspirin and other salicylates should be avoided in this population. Instead, acetaminophen or ibuprofen can be used. This syndrome is known to affect various organs throughout the body including fatty changes in the liver. As the child’s liver begins to fail, lab results may show increased liver enzymes, such as AST, ALT, and increased ammonia levels. Reye’s syndrome is characterized by acute encephalopathy. Children should be monitored closely for signs of increasing ICP, such as a change in level of consciousness, headache, vomiting, abnormal/asymmetrical pupils, posturing, and/or seizures. Early detection and treatment of Reye’s syndrome is essential, as death may result within hours if left untreated.
Play Video + QuizQuestion 1 |
Influenza A causes yearly epidemics and occasional worldwide pandemics, while influenza B causes only seasonal epidemics. Which of the following mechanisms explains the ability of influenza A to cause pandemics?
Antigenic drift from point mutations in hemagglutinin and neuraminidase Hint: Antigenic drift (small point mutations) occurs in both influenza A and B and causes the yearly seasonal epidemics that require an updated vaccine each year. | |
Antigenic shift from reassortment of hemagglutinin or neuraminidase genes | |
Integration of viral DNA into the host genome Hint: Influenza is an RNA virus that does not integrate into host DNA; integration is a feature of retroviruses such as HIV. | |
Latency in sensory ganglia with periodic reactivation Hint: Latency and reactivation are features of herpesviruses (HSV, VZV), not influenza. | |
Production of an exotoxin that inactivates ciliated cells Hint: Pertussis toxin and tracheal cytotoxin damage ciliated cells in Bordetella pertussis infection; influenza does not produce an exotoxin. |
Influenza is a segmented RNA virus. Antigenic shift is a major change in the hemagglutinin (H) or neuraminidase (N) subtype, usually from reassortment of gene segments between human and animal (avian or swine) influenza A viruses. Because the population has no immunity to the new subtype, shift causes pandemics and occurs only in influenza A, which has animal reservoirs. Antigenic drift (point mutations) occurs in A and B and causes the yearly epidemics. Influenza spreads by respiratory droplets, peaks in winter, and causes the most complications in adults 65 and older, children younger than 2 (especially under 6 months), pregnant and postpartum people, residents of long-term care facilities, and people with chronic heart, lung, kidney, liver, metabolic or neurologic disease, immunosuppression or a BMI of 40 or more.
Question 2 |
A 70-year-old woman with COPD presents in January with 1 day of abrupt fever, chills, myalgias, headache and dry cough. Temperature is 38.9°C (102.0°F) and oxygen saturation is 95% on room air. Which of the following is the most appropriate test to confirm the suspected diagnosis?
Chest radiograph Hint: A chest radiograph looks for pneumonia but does not identify influenza. | |
Nasopharyngeal swab for rapid molecular assay (influenza PCR) | |
Paired acute and convalescent influenza serology Hint: Serology takes weeks and does not guide treatment. | |
Rapid influenza antigen test Hint: Rapid antigen tests are fast but have low sensitivity; a negative result does not rule out influenza. | |
Viral culture Hint: Culture is accurate but takes days and is used for public health surveillance, not clinical decisions. |
When influenza testing will change management (high-risk or hospitalized patients), the preferred test is a nasopharyngeal swab for a rapid molecular assay or RT-PCR, which is highly sensitive and specific and returns results in minutes to hours. Rapid antigen tests have low sensitivity, so a negative result does not exclude influenza. Testing should never delay treatment: antivirals are started empirically in high-risk, hospitalized or severely ill patients with suspected influenza during flu season.
Question 3 |
An 85-year-old nursing home resident with heart failure develops abrupt fever, cough, sore throat, headache and myalgias. Temperature is 38.9°C (102.0°F) and oxygen saturation is 95% on room air. A rapid molecular assay is positive for influenza B. Her symptoms began 3 days ago. Which of the following is the most appropriate treatment?
Acyclovir Hint: Acyclovir treats herpes simplex and varicella-zoster infections, not influenza. | |
Amantadine Hint: Amantadine is no longer recommended because of widespread resistance and has no activity against influenza B. | |
No antiviral, because symptoms began more than 48 hours ago Hint: High-risk and hospitalized patients are treated regardless of symptom duration; the 48-hour window matters only for healthy, low-risk outpatients. | |
Oseltamivir | |
Zanamivir Hint: Inhaled zanamivir can cause bronchospasm and is avoided in chronic lung disease; it is impractical for a frail older adult and is not preferred over oseltamivir. |
Oseltamivir, an oral neuraminidase inhibitor active against influenza A and B, is the preferred treatment, usually for 5 days. Treat anyone at high risk for complications (age 65 or older, nursing home residents, chronic heart or lung disease, pregnancy, immunosuppression), anyone hospitalized and anyone with severe or progressive illness regardless of how long symptoms have lasted; benefit is greatest within 48 hours. Healthy low-risk outpatients may be treated if seen within 48 hours. Alternatives: single-dose oral baloxavir (not for severe illness or immunocompromise), inhaled zanamivir (avoid in asthma or COPD) and IV peramivir. Adamantanes (amantadine, rimantadine) are not used. The most common side effect of oseltamivir is nausea, reduced by taking it with food.
Question 4 |
Two residents on the same unit of a long-term care facility develop laboratory-confirmed influenza A within 48 hours of each other. A 78-year-old resident on that unit is asymptomatic and received this season's influenza vaccine 2 months ago. Which of the following is the most appropriate management for this resident?
Amantadine prophylaxis Hint: Amantadine and rimantadine are not recommended because circulating influenza A strains are resistant. | |
Influenza vaccine booster dose Hint: A second vaccine dose is not given to adults, and protection would take 2 weeks to develop. | |
No intervention, because she was vaccinated this season Hint: Vaccination does not exclude a resident from outbreak prophylaxis; antivirals are given to all non-ill residents on the affected unit regardless of vaccination status. | |
Observation and treatment only if symptoms develop Hint: During a facility outbreak, antiviral chemoprophylaxis for all non-ill residents is recommended to stop spread. | |
Oseltamivir chemoprophylaxis |
When influenza is confirmed in a long-term care facility (2 or more residents ill within 72 hours, at least one laboratory-confirmed), all non-ill residents on the affected unit receive oseltamivir chemoprophylaxis once daily, regardless of vaccination status, for at least 2 weeks and until 1 week after the last new case. Unvaccinated residents and staff should also be vaccinated. Baloxavir is not used for facility outbreak prophylaxis, and adamantanes are not recommended. Annual inactivated or recombinant influenza vaccination for everyone 6 months and older remains the main prevention, with a high-dose, adjuvanted or recombinant vaccine preferred for adults 65 and older.
|
List |
References: Merck Manual · UpToDate