

 Lecture

The adult patient (now the most common) will present as → a 45-year-old man with one to two days of severe sore throat and painful swallowing out of proportion to a normal-appearing oropharynx. He has a muffled "hot potato" voice, fever, and tenderness over the anterior neck at the hyoid. He is vaccinated, and stridor and drooling are absent — their appearance would signal impending airway obstruction.
 To watch this and all of Joe-Gilboy PA-C's video lessons you must be a member. Members can log in here or join now.
Epiglottitis is a rapidly progressive bacterial infection of the epiglottis and supraglottic tissues that can cause sudden, complete airway obstruction — a medical emergency
- Hib is the classic cause in unvaccinated children and under-vaccinated regions (Hib vaccine at 2, 4, ± 6 months + booster at 12–15 months) — in the vaccine era, most cases are Streptococcus pneumoniae, group A strep, and Staph aureus (including MRSA), and epiglottitis is now more common in adults
- Key test clue: severe throat pain with minimal oropharyngeal findings + drooling/stridor = epiglottitis until proven otherwise
- Tripod or "sniffing" posture (sitting forward, neck extended to maximize the airway)
- vs. croup — epiglottitis is abrupt, high fever, toxic, drooling, no cough; croup has a barking cough, hoarseness, and the steeple sign
- Dysphagia
- Drooling
- Respiratory Distress
High suspicion or an unstable patient goes straight to the OR — laryngoscopy is the definitive diagnosis (edematous, "cherry-red" epiglottis) and secures the airway in the same controlled setting
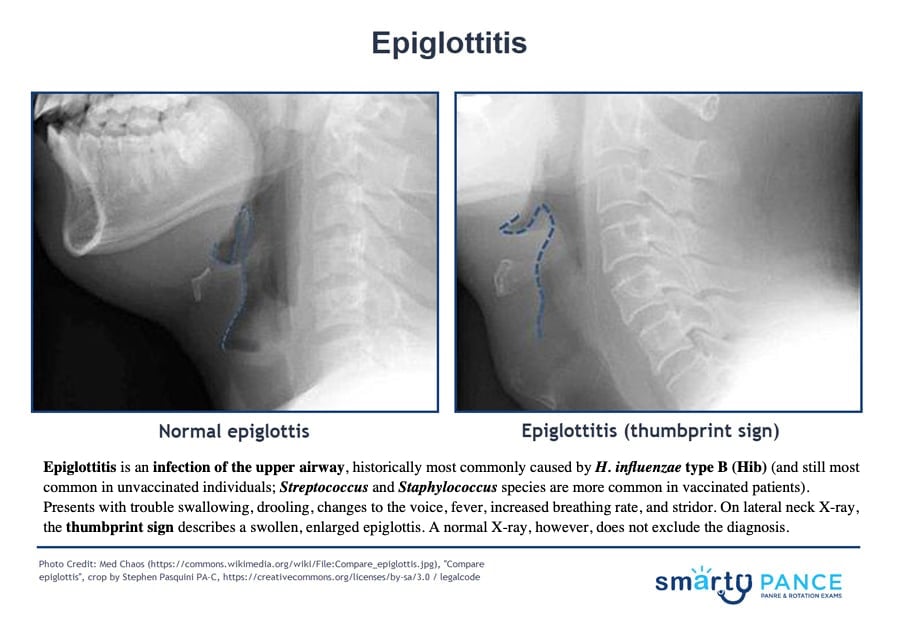
- Stable patients only: lateral neck X-ray → classic thumbprint sign; never send an unstable patient to radiology, and avoid CT — lying flat can obstruct the airway
- Blood and epiglottic cultures after the airway is secured

Airway management, first and foremost — anticipate tracheal intubation in a controlled setting (OR, with ENT/anesthesia); if intubation is impossible, needle or surgical cricothyroidotomy
- ⚠️ Keep the child calm — no tongue-depressor throat exam, no IV sticks, no supine positioning until the airway is secure — agitation can precipitate complete obstruction
- Once the airway is stable: third-generation cephalosporin (ceftriaxone or cefotaxime) + vancomycin (covers MRSA) for 7 to 10 days; corticosteroids are often given to reduce swelling, though evidence is limited
- All patients are admitted (usually ICU) for airway monitoring — never outpatient
- Prevention — Hib immunization; rifampin prophylaxis for ALL household members when Hib is the cause and the home includes an under-immunized child younger than 4, an infant without a completed primary series, or an immunocompromised child
 Osmosis |
|
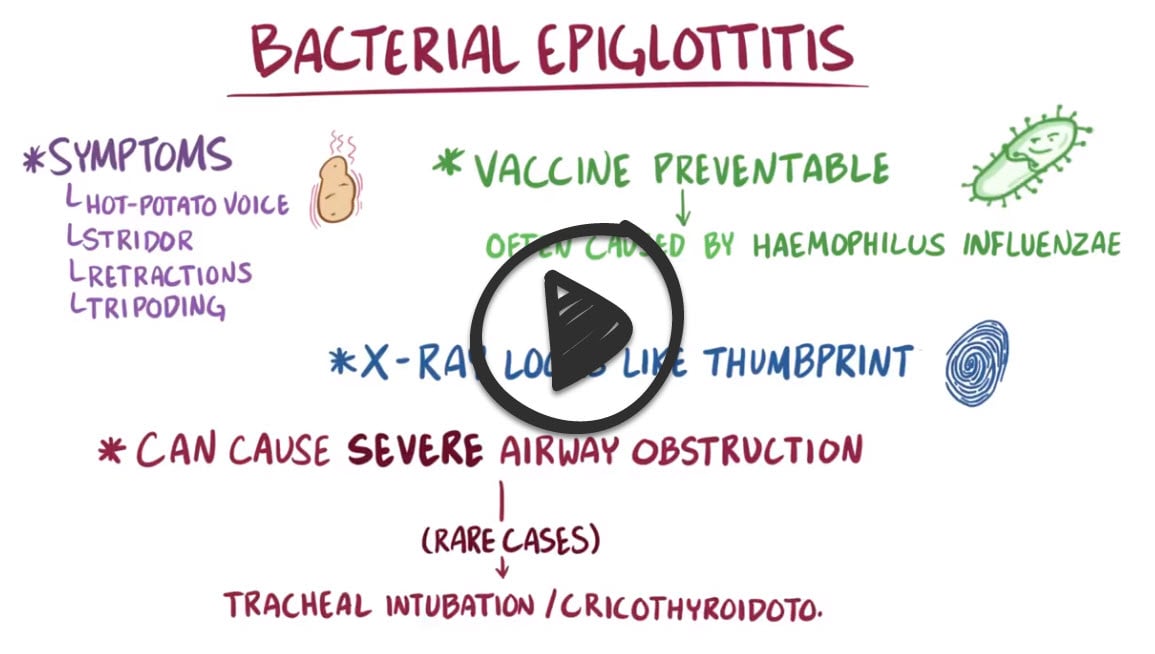 |

Epiglottitis is supraglottic inflammation/obstruction of the airway historically due to infection with Haemophilus influenzae. The Hib vaccine is available to protect against Haemophilus influenzae type b and should be given to infants in three to four divided doses starting at the age of two months. Signs and symptoms of epiglottitis include inspiratory stridor, restlessness, cough, dyspnea, fever, and drooling. It is important to note that the throat should not be examined if epiglottitis is suspected, as this could cause spasm and complete closure of the airway. Assessment of the throat should only be done when immediate endotracheal intubation is possible. Epiglottitis requires emergency treatment.
Epiglottitis Interventions


Question 1 |
A 3-year-old girl who has never been vaccinated develops a sudden high fever over a few hours, then drooling, a muffled voice and difficulty swallowing. She sits leaning forward with her neck extended and appears toxic. She has no cough. Which of the following is the most likely cause?
Bordetella pertussis Hint: Pertussis causes paroxysmal cough with an inspiratory whoop, not drooling and toxicity. | |
Haemophilus influenzae type b | |
Parainfluenza virus Hint: Parainfluenza causes croup: a gradual onset with a barking cough and hoarseness in a nontoxic child. | |
Respiratory syncytial virus Hint: RSV causes bronchiolitis with wheezing and crackles in infants. | |
Staphylococcus aureus Hint: S. aureus is the most common cause of bacterial tracheitis and is now a cause of epiglottitis, but in an unvaccinated child Hib remains the classic cause. |
Epiglottitis (supraglottitis) is a rapidly progressive bacterial cellulitis of the epiglottis and surrounding structures. The classic cause is Haemophilus influenzae type b, now rare because of Hib vaccination and seen mainly in unvaccinated or under-vaccinated children. In vaccinated children and adults no single organism dominates: Streptococcus pneumoniae, group A strep, Staphylococcus aureus (including MRSA) and non-typeable H. influenzae. Clues are the 4 Ds: drooling, dysphagia, dysphonia (muffled "hot potato" voice) and distress, abrupt high fever, a toxic appearance and the tripod or sniffing position. Unlike croup, there is usually no barking cough.
Question 2 |
A 45-year-old man presents with 12 hours of severe sore throat, painful swallowing, fever and a muffled voice. Pharyngeal examination is nearly normal, but he has marked tenderness over the anterior neck at the hyoid. He is breathing comfortably with no stridor. A lateral neck radiograph is obtained. Which of the following findings is most consistent with the suspected diagnosis?
Air-fluid level in the retropharyngeal space Hint: A widened prevertebral soft tissue space or air-fluid level suggests retropharyngeal abscess. | |
Normal soft tissues of the neck Hint: A normal radiograph does not rule out epiglottitis if suspicion is high; direct visualization is still needed. | |
Radiopaque object in the trachea Hint: A radiopaque object suggests a foreign body. | |
Steeple sign of the subglottic trachea Hint: The steeple sign (subglottic narrowing on an AP film) is seen with croup. | |
Thumbprint sign of an enlarged epiglottis |
In epiglottitis the lateral neck radiograph shows a swollen epiglottis, the thumbprint sign, with thickened aryepiglottic folds. The definitive diagnosis is direct visualization of a swollen, cherry-red epiglottis, usually by flexible laryngoscopy performed by an experienced clinician in a controlled setting with airway equipment ready. Radiographs are obtained only in stable patients and must never delay airway management; in a child with suspected epiglottitis, avoid a tongue depressor, IV placement or lying the child down until the airway team is present. Adults often present with sore throat and odynophagia out of proportion to the pharyngeal examination.
Question 3 |
A 4-year-old unvaccinated boy has a sudden high fever, drooling, a muffled voice and inspiratory stridor. He is sitting upright, leaning forward, and is anxious but maintaining his airway. Oxygen saturation is 95% on room air. Which of the following is the most appropriate next step?
Examine the pharynx with a tongue depressor Hint: A tongue depressor can provoke laryngospasm and complete airway obstruction. | |
Keep him calm with a parent and arrange airway control in the operating room by anesthesia and ENT | |
Nebulized racemic epinephrine Hint: Racemic epinephrine helps croup but has no proven benefit in epiglottitis and may agitate the child. | |
Obtain an IV line and blood cultures before anything else Hint: Painful procedures can agitate the child and cause obstruction; they wait until the airway is secured. | |
Place him supine for a portable chest radiograph Hint: Lying supine can cause the swollen epiglottis to obstruct the airway. |
Airway first. A child with suspected epiglottitis is kept calm and upright on the parent's lap with blow-by oxygen; avoid a tongue depressor, IV attempts, blood draws and lying down. The airway team (anesthesia and ENT) is called immediately, and the airway is secured by intubation in the operating room (children younger than 6 years are intubated even without severe distress). If the child stops maintaining the airway, give bag-mask ventilation with 100% oxygen until intubation, and use needle or surgical cricothyrotomy if intubation fails. Antibiotics and cultures follow once the airway is secure.
Question 4 |
A 5-year-old boy with epiglottitis has just been intubated in the operating room. Blood cultures are drawn. He has no drug allergies. Which of the following is the most appropriate empiric antibiotic regimen?
Intravenous ceftriaxone plus vancomycin | |
Intravenous gentamicin Hint: Aminoglycosides do not cover the main causes of epiglottitis. | |
Intravenous metronidazole Hint: Metronidazole covers anaerobes only. | |
Oral amoxicillin Hint: Oral therapy is not appropriate for a life-threatening infection in an intubated child, and amoxicillin misses beta-lactamase producing H. influenzae and MRSA. | |
Oral azithromycin Hint: Macrolides do not reliably cover Hib, pneumococcus or MRSA. |
After the airway is secured, every patient with epiglottitis receives intravenous ceftriaxone (or cefotaxime) plus vancomycin to cover H. influenzae type b, Streptococcus pneumoniae, group A strep and Staphylococcus aureus including MRSA, for 7 to 10 days total. Adults are usually also given IV dexamethasone. Household contacts of a child with invasive Hib disease may need rifampin prophylaxis.
Question 5 |
A 3-year-old unvaccinated girl is hospitalized with epiglottitis, and blood cultures grow Haemophilus influenzae type b. She lives with her parents and a 2-year-old brother who has received only 1 dose of Hib vaccine. Which of the following is the most appropriate management for the household?
Hib vaccine for the brother only, without antibiotics Hint: Catching up the brother's vaccines is also needed, but vaccination alone does not clear carriage; the household needs rifampin. | |
No intervention unless someone develops symptoms Hint: Close contacts of invasive Hib disease are at increased risk, and prophylaxis is given before symptoms. | |
Oral amoxicillin for the brother only Hint: Amoxicillin does not eradicate nasopharyngeal carriage of Hib. | |
Rifampin for all household members, including adults | |
Rifampin for the brother only Hint: When an under-immunized child younger than 4 lives in the home, all household members receive rifampin, not only the child. |
After a case of invasive Hib disease, rifampin prophylaxis is given to all household members, regardless of age or vaccination status, when the home includes a child younger than 4 years who is not fully immunized, a child younger than 12 months who has not finished the primary series, or an immunocompromised child. The index patient also receives rifampin before discharge unless treated with ceftriaxone or cefotaxime. Under-immunized children in the home should also get their Hib vaccines. If no such high-risk child lives in the home, prophylaxis is not needed.
|
List |
References: Merck Manual · UpToDate