

 Lecture

Patient will present as → a 38-year-old African-American woman who visits the clinic complaining of persistent dry cough, shortness of breath, and mild chest pain for the past two months. She also notes occasional fevers and unexplained weight loss. You note erythema nodosum on her lower legs. Her chest X-ray reveals bilateral hilar lymphadenopathy and reticular opacities. Pulmonary function tests show a restrictive lung disease pattern. Laboratory findings include elevated serum angiotensin-converting enzyme (ACE) levels. A biopsy of the lymph nodes obtained during bronchoscopy demonstrates noncaseating granulomas, consistent with a diagnosis of sarcoidosis.

To watch this and all of Joe-Gilboy PA-C's video lessons, you must be a member. Members can log in here or join now.
Sarcoidosis is a systemic granulomatous disease characterized by noncaseating (non-necrotizing) granulomas that can involve multiple organ systems
- The condition usually presents between ages 20 and 60 (more than half of cases are diagnosed after age 40; women are affected about twice as often) and is most common in Northern Europeans and African Americans
- Sarcoidosis is caused by an abnormal T-cell–mediated immune response to an unknown environmental antigen in a genetically susceptible host, leading to the formation of non-caseating granulomas
- Certain individuals appear to have a genetic predisposition, and exposure to bacterial or viral antigens, organic dusts, or inorganic particles may act as the triggering stimulus
- Clinical presentation is variable. Fever, weight loss, arthralgias, and erythema nodosum (more common in Europeans) are typical early systemic features, while cough and dyspnea may be mild or even absent despite significant pulmonary involvement
- Bilateral hilar and mediastinal lymphadenopathy on chest radiograph is the hallmark finding and is present in up to 90% of cases
- Sarcoidosis causes elevated ACE and hypercalcemia because activated macrophages within granulomas produce ACE and convert inactive vitamin D into its active form, increasing intestinal calcium absorption

"If you see hilar lymphadenopathy, it is right to think Sarcoidosis, but not always. Here is a rough guide to approaching hilar adenopathy:
- Young female = Sarcoidosis
- Young kid with a fever, from Ohio, zookeeper = histoplasmosis
- Old guy in his 60's works on ceramics = Berylliosis"
Other manifestations include hepatic granulomas, granulomatous uveitis, polyarthritis, cardiac symptoms (including angina, CHF, and conduction abnormalities), cranial nerve palsies, and diabetes insipidus. Lupus pernio (violaceous plaques on the nose, cheeks, ears, and lips) is the most specific skin lesion; erythema nodosum is the most common
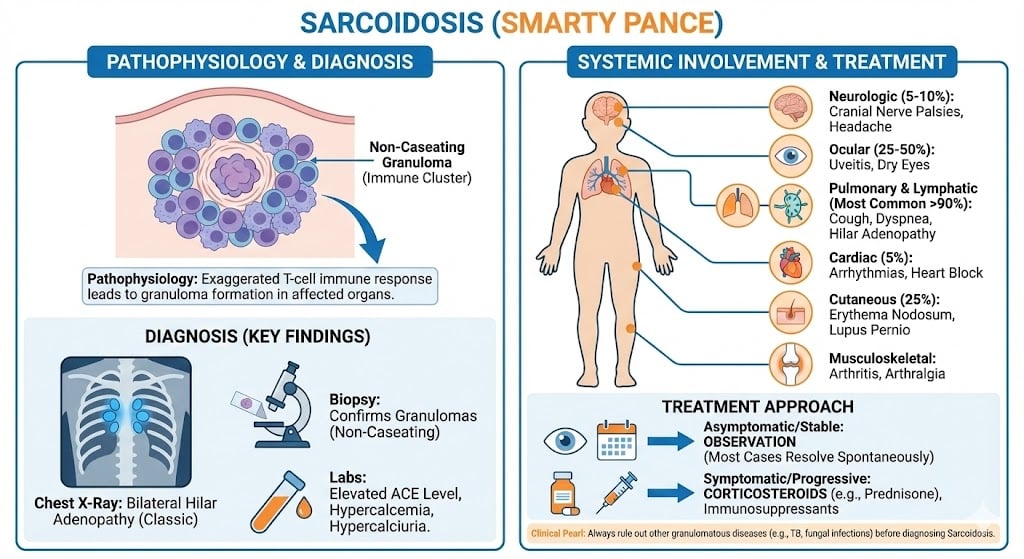
Blood tests may show hypercalciuria (30–50% of patients), hypercalcemia (10–20%), and an elevated serum ACE level — but ACE is not sensitive or specific enough to diagnose or rule out sarcoidosis
- ESR is often elevated
- Laboratory findings include leukopenia, hypercalcemia, hypercalciuria, and hypergammaglobulinemia (particularly in African American patients)
- Other abnormalities include elevated uric acid (not usually associated with gout), elevated alkaline phosphatase, elevated gamma-glutamyl transpeptidase, elevated levels of ACE, and pulmonary function tests showing restriction and impaired diffusing capacity
- Diagnosis = compatible clinical and imaging findings + noncaseating granulomas on biopsy + exclusion of other causes (tuberculosis, fungal infection, lymphoma)
- Biopsy the most accessible site (skin lesion, peripheral lymph node); for hilar or mediastinal nodes, endobronchial ultrasound-guided transbronchial needle aspiration (EBUS-TBNA) is the preferred first sampling procedure (mediastinoscopy if it is nondiagnostic)
- No biopsy is needed for classic Löfgren syndrome (erythema nodosum + bilateral hilar adenopathy + fever or ankle arthritis) once infection is excluded; biopsy can often be deferred in asymptomatic bilateral hilar adenopathy with close follow-up
- FDG-PET can locate active disease and biopsy targets (gallium scanning is largely historical)
- Baseline screening for every patient: ECG (cardiac sarcoidosis), eye exam, serum calcium, creatinine, alkaline phosphatase, CBC, and PFTs with DLCO
Serial pulmonary function tests are important for assessing disease progression and guiding treatment
"Hypercalcemia in sarcoidosis is due to the uncontrolled synthesis of 1,25-dihydroxyvitamin D3 by macrophages. 1,25-dihydroxyvitamin D3 leads to increased absorption of calcium in the intestine and to increased resorption of calcium in the bone."

Treatment for symptomatic patients consists of CORTICOSTEROIDS, methotrexate, and other immunosuppressive medications if steroid therapy is not helpful
- Many patients need no treatment — asymptomatic disease (especially stage I) often remits on its own; follow symptoms, PFTs, and imaging
- Treat when there are troublesome symptoms, declining lung function, or organ-threatening disease (heart, eyes, nervous system, hypercalcemia): oral corticosteroids (prednisone) work fastest and are the classic first-line drug; for severe or progressive disease that will need long-term treatment, methotrexate is now often preferred (alone, or with prednisone if disease is progressing rapidly) to limit steroid side effects
- Methotrexate is the main steroid-sparing agent; TNF inhibitors (infliximab) are reserved for refractory disease
- Löfgren syndrome is usually self-limited — treat with NSAIDs
The prognosis depends on the severity of the disease. Spontaneous improvement is common; however, significant disability can occur with multiorgan involvement
- Pulmonary fibrosis (with respiratory failure and pulmonary hypertension) is the leading cause of death; cardiac sarcoidosis (heart block, ventricular arrhythmias, sudden death) is the next most important
 Osmosis |
|
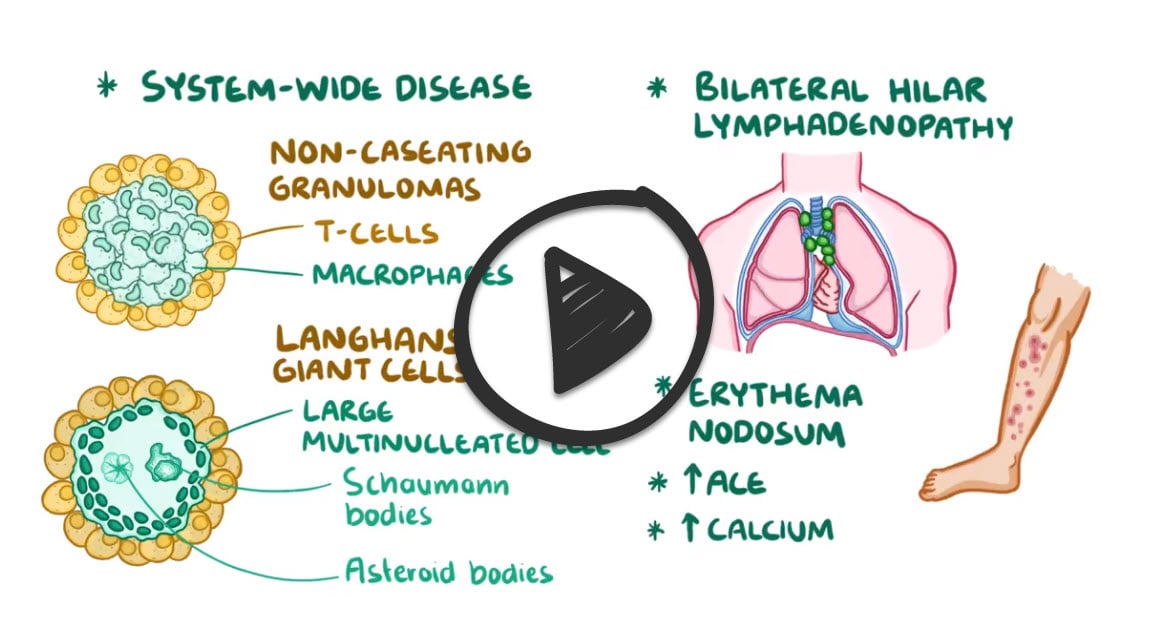 |

Sarcoidosis is a granulomatous disease of unknown cause (an exaggerated immune response) characterized by noncaseating granulomas throughout the body. It is characterized by laboratory findings such as elevated ACE levels and asteroid bodies. Due to vitamin D activation, hypercalcemia is present. This disease is often asymptomatic and is diagnosed after finding bilateral hilar lymphadenopathy on a routine X-ray.
Play Video + QuizQuestion 1 |
Ectopic parathyroid hormone–related peptide secretion Hint: PTHrP (classically from squamous cell lung cancer) suppresses calcitriol; it would not raise 1,25-dihydroxyvitamin D. | |
Excess dietary vitamin D intake Hint: Vitamin D intoxication mainly raises 25-hydroxyvitamin D; nothing in her history suggests excess intake. | |
Granuloma macrophage 1-alpha-hydroxylase activity | |
Osteolytic bone metastases Hint: Osteolytic metastases release calcium from bone with a low, not high, 1,25-dihydroxyvitamin D level. | |
Parathyroid adenoma Hint: A parathyroid adenoma causes hypercalcemia with a HIGH PTH; her PTH is suppressed. |
Question 2 |
Endobronchial ultrasound-guided node aspiration | |
Gallium-67 scan Hint: Gallium scanning is largely historical (FDG-PET has replaced it) and cannot confirm the diagnosis without tissue. | |
Mediastinoscopy with lymph node biopsy Hint: Mediastinoscopy is more invasive and is reserved for when endoscopic sampling is nondiagnostic or not possible. | |
Serum angiotensin-converting enzyme level Hint: Serum ACE is not sensitive or specific enough to diagnose or rule out sarcoidosis. | |
Video-assisted thoracoscopic lung biopsy Hint: Surgical lung biopsy is far more invasive and is rarely needed when enlarged nodes can be sampled endoscopically. |
Question 3 |
Infliximab Hint: TNF inhibitors such as infliximab are reserved for disease that is refractory to corticosteroids and a steroid-sparing agent. | |
Inhaled albuterol Hint: A bronchodilator does not treat granulomatous inflammation. | |
Nintedanib Hint: Nintedanib is an antifibrotic for progressive pulmonary fibrosis; it is not the initial treatment for active granulomatous sarcoidosis. | |
Oral prednisone | |
Pirfenidone Hint: Pirfenidone is an antifibrotic for idiopathic pulmonary fibrosis, not sarcoidosis. |
Question 4 |
Endobronchial ultrasound-guided node aspiration Hint: Classic Löfgren syndrome is a clinical diagnosis; biopsy is not needed once infection is excluded. | |
Methotrexate Hint: Methotrexate is a steroid-sparing agent for chronic, progressive disease — not for self-limited Löfgren syndrome. | |
Nonsteroidal anti-inflammatory drug | |
Oral prednisone Hint: Corticosteroids are reserved for severe symptoms that do not respond to NSAIDs. | |
Surgical mediastinal node biopsy Hint: A surgical biopsy is unnecessary for this classic, self-limited presentation. |
Question 5 |
Acute coronary syndrome Hint: Acute coronary syndrome typically presents with acute chest pain and diaphoresis, not months of conduction disease and heart failure in a young patient with sarcoidosis. | |
Cardiac sarcoidosis | |
Cryptogenic organizing pneumonia Hint: Cryptogenic organizing pneumonia presents with cough, fever, and patchy consolidation — it does not cause conduction disease or cardiomegaly. | |
Hypertensive encephalopathy Hint: Hypertensive encephalopathy causes headache, vomiting, and confusion with severely elevated blood pressure. | |
Pneumoconiosis Hint: Pneumoconiosis requires a mineral-dust exposure history and does not cause conduction disease. |
|
List |
References: Merck Manual · UpToDate