

 Lecture

Patient will present with → a 38-year-old nonsmoking woman who comes to the clinic with a persistent cough and recurrent pneumonia in the same lobe (the right middle lobe, three times in the past year), along with several episodes of blood-streaked sputum. She was told she has asthma, but inhalers have not helped. She denies flushing or diarrhea. On physical examination, there is a localized, fixed wheeze over the right mid-lung field. Chest CT reveals a well-circumscribed central endobronchial mass in the right middle lobe bronchus with post-obstructive atelectasis. Bronchoscopy shows a smooth, pink-purple, highly vascular lesion, and biopsy confirms a typical carcinoid tumor (chromogranin A positive).

To watch this and all of Joe-Gilboy PA-C's video lessons you must be a member. Members can log in here or join now.

"Symptoms of carcinoid syndrome can be memorized using the mnemonic FDR (flushing, diarrhea, and right-sided heart valves)."
A tumor arising from neuroendocrine cells → leading to excess secretion of serotonin, histamine, and bradykinin
- Common primary sites include GI (small and large intestines, stomach, pancreas, liver), lungs, ovaries, and thymus
- The most common site for a neuroendocrine (carcinoid) tumor to metastasize to is the liver
- The small intestine (ileum) is the most common source of carcinoid syndrome, which appears once the tumor has spread to the liver; lung carcinoids are usually primary bronchial tumors, not metastases from the gut
- Usually asymptomatic until liver metastasis; symptoms develop occasionally
- GI tract tumor→ hormone secretion → enter the portal circulation → liver inactivates hormones → no symptoms
- Liver tumor → hormone secretion → released into circulation + liver dysfunction → symptoms
- Carcinoid syndrome (the hallmark sign) = Cutaneous flushing, diarrhea, wheezing and low blood pressure is actually quite rare and occurs in ~ 5% of carcinoid tumors and becomes manifest when vasoactive substances from the tumors enter the systemic circulation, escaping hepatic degradation.
- The syndrome includes flushing, ↑ intestinal motility (diarrhea), itching and less frequently, heart failure, vomiting, bronchoconstriction, asthma, and wheezing
- ↑ Serotonin leads to collagen fiber thickening, fibrosis = heart valve dysfunction → tricuspid regurgitation, pulmonary stenosis/bronchoconstriction, and wheezing
- ↑ Histamine and bradykinin = vasodilation and flushing
- ↑ serotonin synthesis → ↓ tryptophan → ↓ niacin/B3 synthesis = pellagra
CT-Scan to locate the tumors
- Somatostatin receptor imaging (Ga-68 DOTATATE PET, which has replaced the older Octreoscan) → a radiolabeled somatostatin analog binds to somatostatin receptors on tumor cells
- 24-hour urine 5-hydroxyindoleacetic acid (5-HIAA) → the main metabolite of serotonin; best initial test when carcinoid syndrome is suspected (it can be normal with bronchial carcinoids)
- Pellagra (niacin/B3 deficiency) - ↑ serotonin synthesis → ↓ tryptophan → ↓ niacin/B3 synthesis
- CT of the chest shows a well-circumscribed central endobronchial mass, often with post-obstructive atelectasis or pneumonia
- Bronchoscopy with biopsy confirms the diagnosis: a pink/purple, well-vascularized central lesion
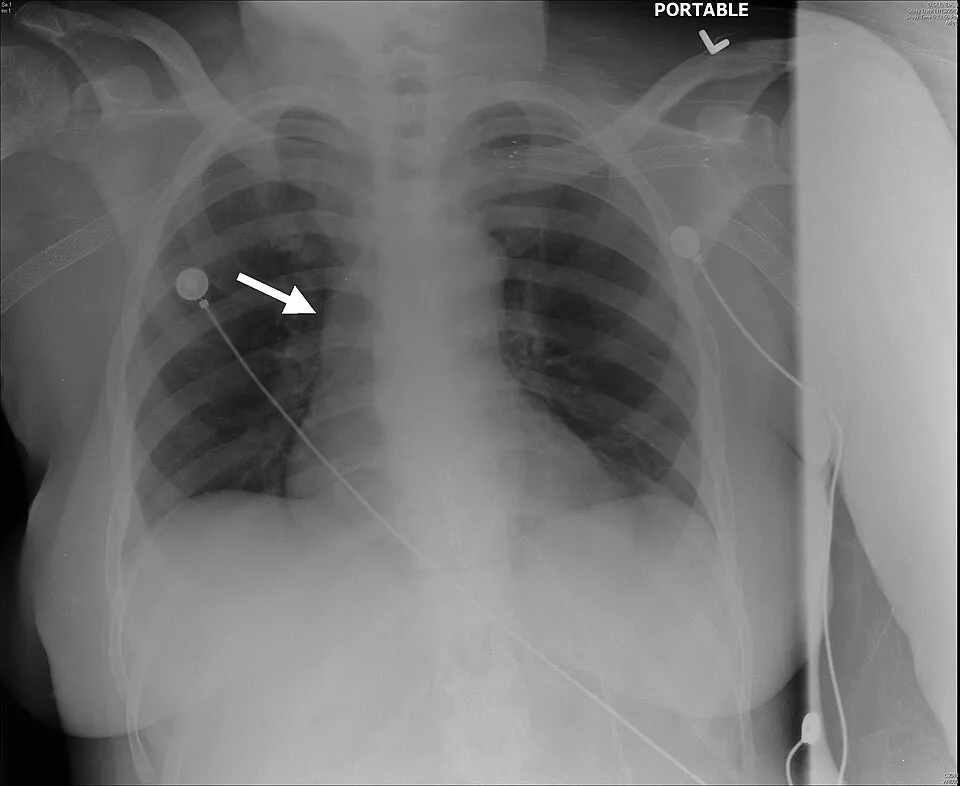
Carcinoid tumors are usually centrally located, arising in large airways. The arrow points to the tumor in the right hilar region. Image: Yale Rosen from USA, CC BY-SA 2.0, via Wikimedia Commons.
Treatment is by surgical excision and carries a good prognosis
- The lesions are relatively resistant to radiation therapy and chemotherapy
- Octreotide or lanreotide - somatostatin analogs that bind somatostatin receptors and decrease the secretion of serotonin by the tumor, controlling carcinoid syndrome symptoms
- Niacin supplementation
 Osmosis |
|
 |

Lung carcinoma is typically divided into two categories, small cell carcinoma and non-small cell carcinoma. Non-small cell carcinoma subtypes include adenocarcinoma, squamous cell carcinoma, large cell carcinoma and carcinoid tumor. Bronchial carcinoid tumor is a neuroendocrine tumor that carries an excellent prognosis. It may be asymptomatic or may present with symptoms of bronchial obstruction such as coughing or hemoptysis. Occasionally, bronchial carcinoid tumors may cause carcinoid syndrome which is characterized by flushing, diarrhea, and wheezing. These tumors are chromogranin A positive and histology shows nests of neuroendocrine cells. Additionally, patients will have elevated urine 5-HIAA when carcinoid syndrome is present. Treatment includes surgical resection and octreotide for symptomatic relief.
Play Video + QuizQuestion 1 |
Cheilosis and stomatitis Hint: Riboflavin (vitamin B2) deficiency causes stomatitis, cheilosis, glossitis, and anemia. | |
Confusion, ophthalmoplegia, and ataxia Hint: This triad is Wernicke encephalopathy from thiamine (vitamin B1) deficiency. | |
Dermatitis and mental status change | |
Ptosis, anhidrosis, and miosis Hint: Horner syndrome results from a sympathetic chain lesion, such as a Pancoast tumor. | |
Swollen gums, bruising, and hemarthrosis Hint: Scurvy (vitamin C deficiency) causes bleeding gums, bruising, hemarthrosis, and perifollicular hemorrhages. |
Question 2 |
24-hour urinary 5-hydroxyindoleacetic acid (5-HIAA) | |
Colonoscopy with biopsy Hint: Not indicated unless symptoms suggest a colonic lesion; most tumors causing carcinoid syndrome arise in the small intestine. | |
CT scan of the abdomen and pelvis Hint: Imaging localizes the tumor after biochemical confirmation; it is not the first test. | |
Plasma serotonin level Hint: Plasma serotonin fluctuates and is less reliable than urinary 5-HIAA. | |
Serum chromogranin A level Hint: Sensitive but nonspecific; it is used as an adjunct or to monitor disease, not as the first test. |
Question 3 |
Cisplatin Hint: Cytotoxic chemotherapy has little role in well-differentiated carcinoid tumors. | |
Methysergide Hint: A serotonin antagonist rarely used now because of retroperitoneal fibrosis. | |
Octreotide | |
Ondansetron Hint: An antiemetic; it does not control flushing or diarrhea from carcinoid syndrome. | |
Propranolol Hint: May worsen hypotension and does not treat hormone-mediated symptoms. |
Question 4 |
Bronchial carcinoid tumor | |
Foreign body aspiration Hint: A foreign body can cause recurrent pneumonia in one segment, but bronchoscopy would show the object, not a vascular mass. | |
Pulmonary hamartoma Hint: A benign peripheral nodule with popcorn calcification or fat; it rarely grows inside the airway. | |
Small cell lung cancer Hint: A rapidly growing central cancer of heavy smokers with bulky nodes, not a smooth vascular mass in a young nonsmoker. | |
Squamous cell carcinoma Hint: A central smoking-related cancer of older adults that often cavitates. |
Question 5 |
Combination chemotherapy Hint: Carcinoid tumors respond poorly to chemotherapy, and localized disease is curable with surgery. | |
External beam radiation therapy Hint: Radiation is not curative for a resectable carcinoid tumor. | |
Long-acting octreotide alone Hint: Somatostatin analogs control carcinoid syndrome symptoms or advanced disease; they do not cure a localized tumor. | |
Observation with yearly CT Hint: Observation leaves a curable tumor in place to grow and obstruct the airway. | |
Surgical resection |
|
List |
References: Merck Manual · UpToDate