

Patient will present as → a 45-year-old male with a one-week history of hacking, non-productive cough, low-grade fever, malaise, and myalgias. The chest x-ray reveals widespread bilateral interstitial infiltrates and a nasopharyngeal molecular test is positive for influenza A.Examination reveals scattered rhonchi and rales upon auscultation of the chest.
Adults → The influenza viruses are the most common viral cause of pneumonia
- Primary influenza pneumonia manifests with persistent symptoms of cough, sore throat, headache, myalgia, and malaise for more than three to five days. The symptoms may worsen with time, and new respiratory signs and symptoms, such as dyspnea and cyanosis, appear.
- Bacterial pneumonia complicates approximately 0.5 percent of influenza cases in healthy young individuals and at least 2.5 percent of cases in older individuals and those with predisposing conditions. Bacterial pneumonia typically occurs within a few days of influenza onset
Kids → RSV, 1st episode of wheezing
- Respiratory syncytial virus (RSV) is the most frequent cause of lower respiratory tract infection in infants and children and the second most common viral cause of pneumonia in adults
- Patients with RSV pneumonia typically present with fever, nonproductive cough, otalgia, anorexia, and dyspnea. Wheezes, rales, and rhonchi are common physical findings.
Parainfluenza virus pneumonia
- Parainfluenza virus (PIV) is second in importance only to RSV as a cause of lower respiratory tract disease in children and pneumonia and bronchiolitis in infants younger than 6 months.
- The signs and symptoms include fever, cough, coryza, dyspnea with rales, and wheezing.
Chest radiography usually demonstrates bilateral lung involvement, but none of the viral etiologies of pneumonia result in pathognomonic findings with CXR
- Nasopharyngeal swab for molecular testing (RT-PCR or rapid molecular assay) for influenza, SARS-CoV-2 and RSV; rapid antigen tests have low sensitivity, so a negative result does not rule out influenza
Oseltamivir (Tamiflu) is the preferred antiviral agent for the treatment of influenza
- Alternative antiviral agents for the treatment of uncomplicated influenza include baloxavir (oral single dose), zanamivir (inhaled regimen twice daily for five days), or peramivir (parenteral single dose)
- Amantadine and Rimantadine are adamantanes active only against influenza A, and they are not recommended (widespread resistance) (CDC/IDSA).
Respiratory syncytial virus (RSV) pneumonia
- Ribavirin is reserved for select severely immunocompromised adults (for example, after hematopoietic cell transplant), and the evidence for benefit is limited. For most adults, treatment of RSV pneumonia is supportive. Prevention: one RSV vaccine dose for all adults ≥75 and for adults 50–74 at increased risk (ACIP); nirsevimab or a maternal vaccine protects infants.
Parainfluenza virus (PIV) pneumonia
- Treatment is mainly supportive, but aerosolized and oral ribavirin have been associated with a reduction in PIV shedding and clinical improvement in immunocompromised patients
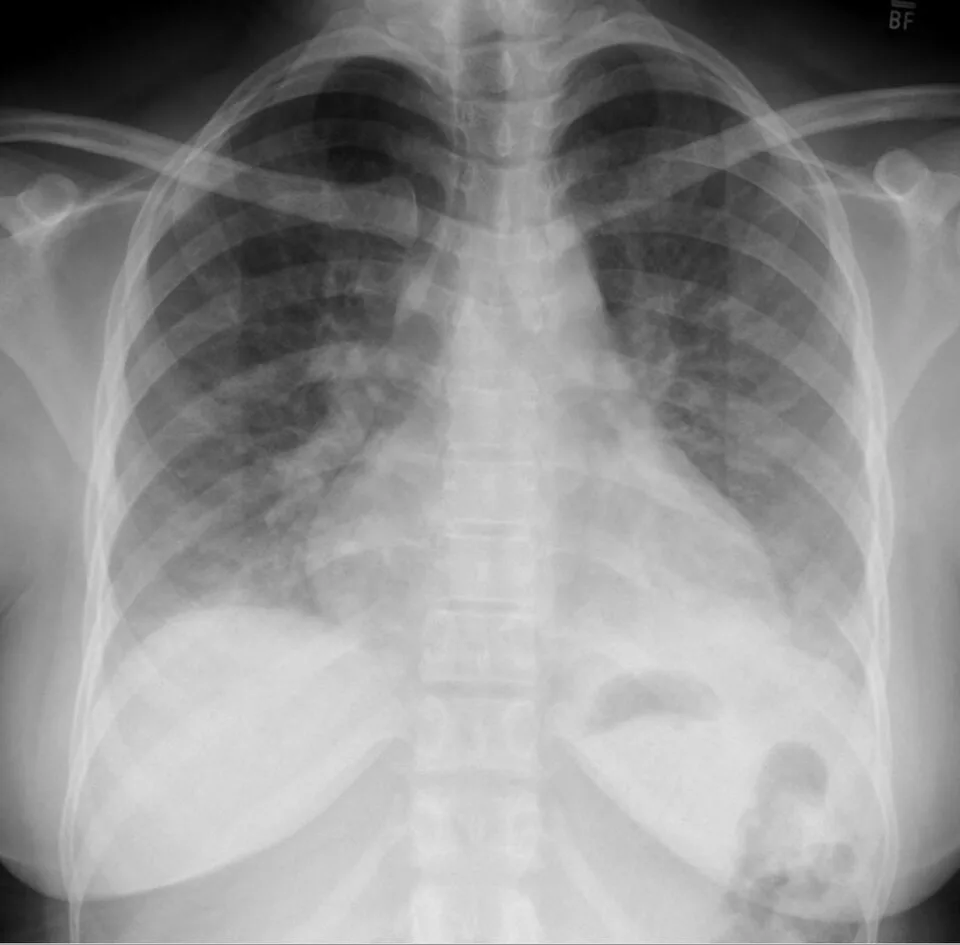
Chest radiograph from a patient with viral pneumonia showing widespread bilateral interstitial infiltrates. Image: Hellerhoff, CC BY-SA 4.0, via Wikimedia Commons.
Question 1 |
A previously healthy 4-month-old infant is brought to the emergency department in January with 3 days of rhinorrhea and cough followed by poor feeding. Temperature is 38.3°C (100.9°F), respiratory rate is 60/min and oxygen saturation is 92% on room air. Examination shows diffuse wheezes and crackles. Chest radiograph shows hyperinflation with patchy interstitial infiltrates. Which of the following is the most likely cause?
Adenovirus Hint: Adenovirus causes pneumonia, conjunctivitis and pharyngitis year-round but is far less common than RSV in young infants. | |
Human metapneumovirus Hint: Human metapneumovirus causes an illness identical to RSV, but it is less common. | |
Parainfluenza virus Hint: Parainfluenza is the classic cause of croup (barking cough, stridor) in children 6 months to 3 years. | |
Respiratory syncytial virus | |
Streptococcus pneumoniae Hint: Pneumococcus causes lobar consolidation with high fever, not diffuse wheezing with interstitial infiltrates. |
Respiratory syncytial virus (RSV) is the most common cause of viral pneumonia and bronchiolitis in infants and young children, peaking in winter. Viruses cause most pneumonia in children younger than 5 years; in adults influenza is the most common viral cause, with RSV, human metapneumovirus, parainfluenza, rhinovirus, adenovirus and SARS-CoV-2 also common. Viral pneumonia typically produces bilateral interstitial or patchy infiltrates, wheeze and crackles, and a gradual onset after an upper respiratory prodrome.
Question 2 |
A 70-year-old woman presents in February with 2 days of fever, myalgias, headache and dry cough. Temperature is 38.9°C (102.0°F), respiratory rate is 22/min and oxygen saturation is 93% on room air. Chest radiograph shows bilateral patchy interstitial infiltrates. Which of the following is the most appropriate test to identify the cause?
Bronchoalveolar lavage with methenamine silver stain Hint: Silver staining of bronchoalveolar lavage fluid is used to diagnose Pneumocystis pneumonia in immunocompromised patients. | |
Cold agglutinin titer Hint: Cold agglutinins are nonspecific and are no longer used to diagnose Mycoplasma or any other pneumonia. | |
Nasopharyngeal swab for respiratory virus nucleic acid amplification (PCR) | |
Paired acute and convalescent viral serology Hint: Paired serology takes weeks and is used only for epidemiology, not to guide treatment. | |
Rapid influenza antigen test Hint: Rapid antigen tests have low sensitivity; a negative result does not rule out influenza, so molecular testing is preferred. |
When viral pneumonia is suspected during respiratory virus season, the test of choice is a nasopharyngeal swab for nucleic acid amplification (RT-PCR or a rapid molecular assay), often as a multiplex panel for influenza, SARS-CoV-2 and RSV. Molecular tests are far more sensitive than rapid antigen tests, so a negative antigen test does not rule out influenza. A positive influenza result in a hospitalized or high-risk patient should prompt antiviral therapy, and treatment should not be delayed while waiting for results.
Question 3 |
Acyclovir Hint: Acyclovir treats herpes simplex and varicella-zoster virus infections; it has no activity against influenza. | |
Amantadine Hint: Amantadine and rimantadine are no longer recommended because circulating influenza A viruses are almost universally resistant, and they have no activity against influenza B. | |
Amoxicillin-clavulanate Hint: Antibacterials are not indicated for uncomplicated influenza; they are added only if secondary bacterial pneumonia is suspected. | |
Oseltamivir | |
Ribavirin Hint: Ribavirin is not used for influenza and is no longer routinely used even for RSV. |
|
List |
References: Merck Manual · UpToDate