

Patient will present as → a 43-year-old woman with a history of COPD presents to your office with worsening dyspnea, especially at rest. She also complains of dull, retrosternal chest pain. On examination, she has persistent widened splitting of S2. Radiographic findings demonstrate peripheral “pruning” of the large pulmonary arteries.
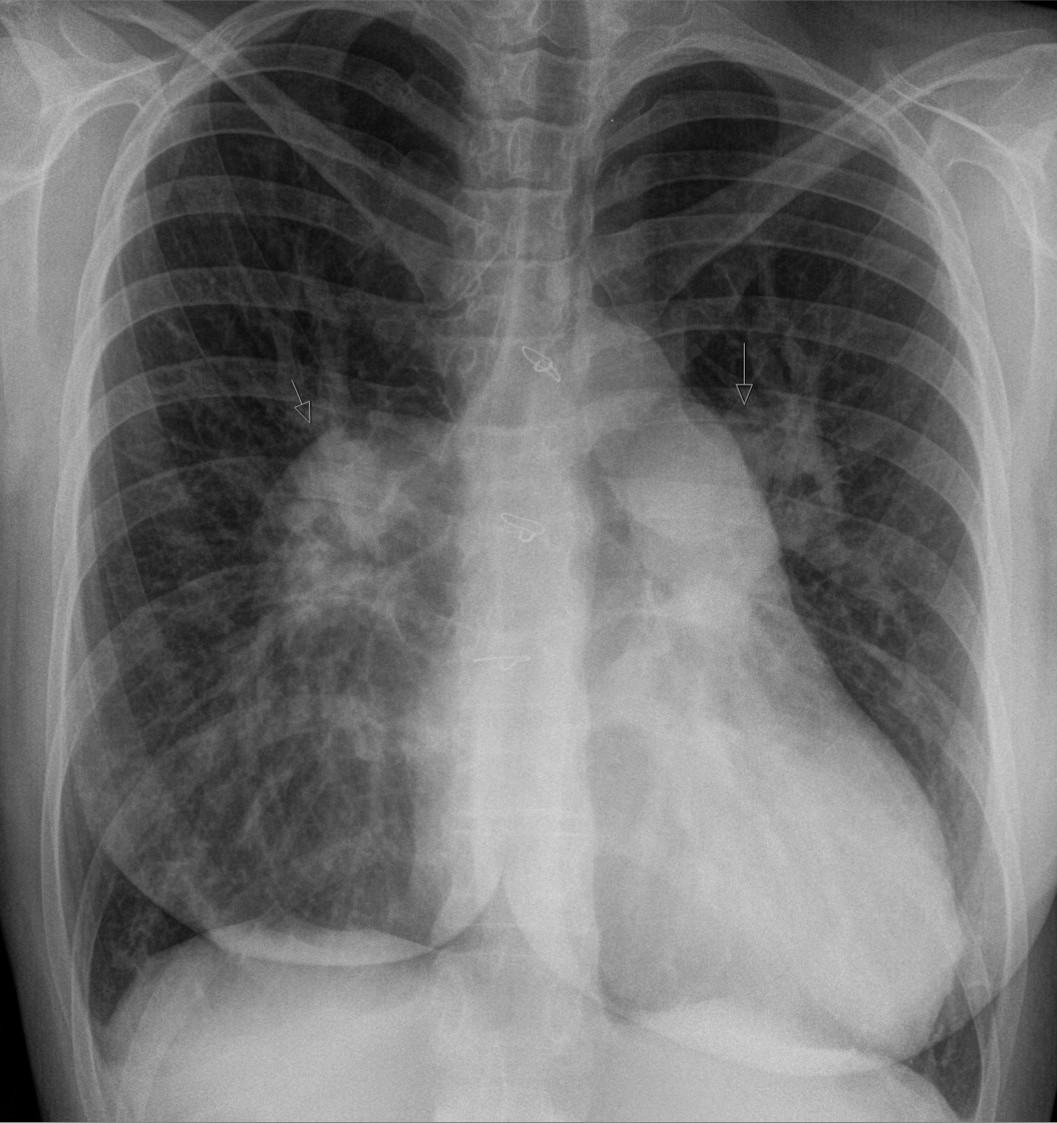
**Peripheral “pruning” of the large pulmonary arteries is characteristic of pulmonary hypertension in severe emphysema
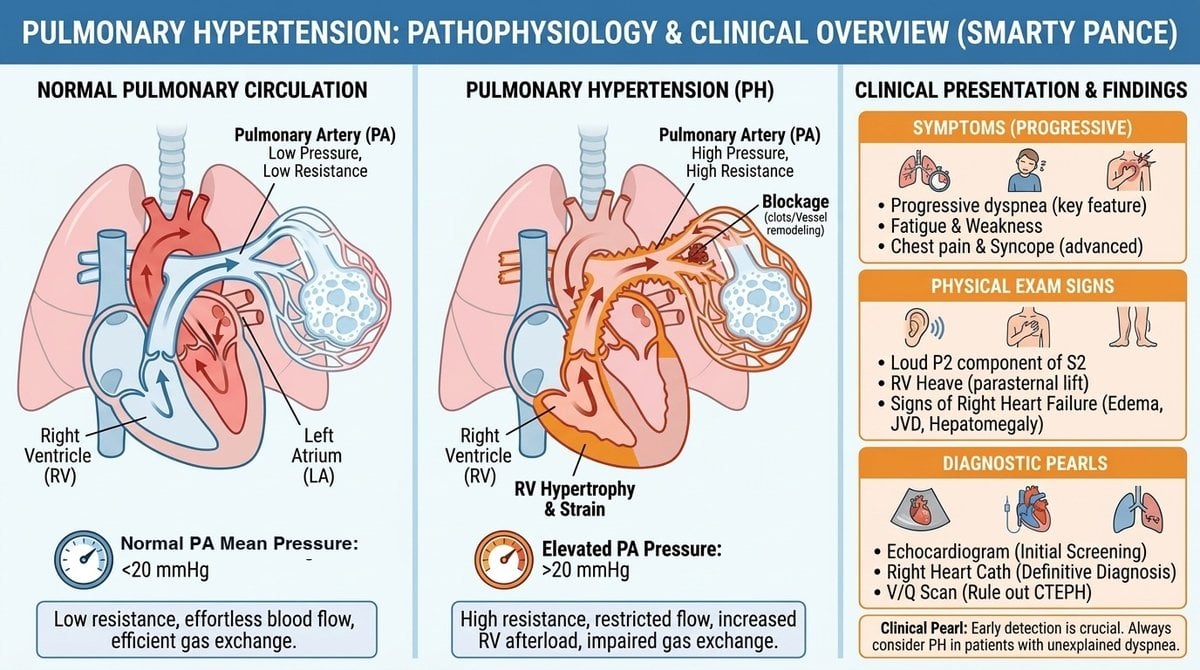 Pulmonary Hypertension (PH) is defined as increased pressure in the pulmonary arteries, leading to right ventricular strain and potential heart failure
- Blood pressure in the lungs is usually very low, 15/5. In pulmonary hypertension, the pressure increases > 20 mmHg at rest
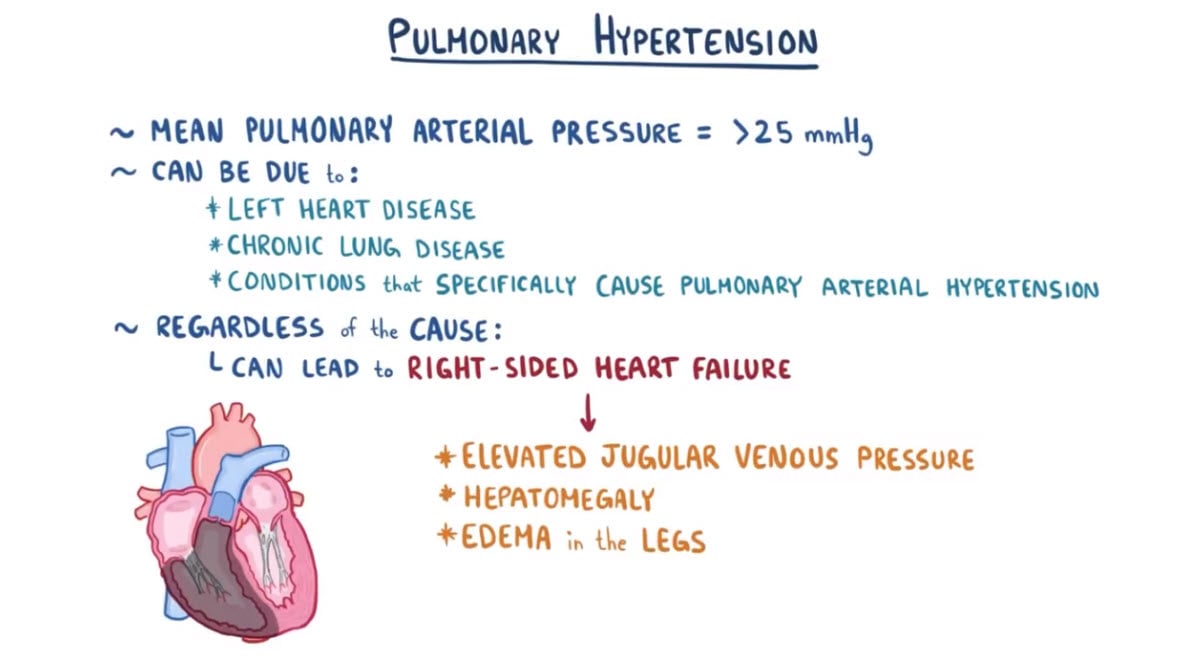
- It can be due to left heart disease, chronic lung disease, or conditions that specifically cause pulmonary arterial hypertension
- Left heart disease (heart failure, especially with preserved ejection fraction) is the most common cause of pulmonary HTN overall. Mitral stenosis is the classic valvular cause: the mitral valve is so tight that blood can’t pass into the left ventricle, which backs pressure up into the lungs
- Symptoms include dyspnea on exertion, fatigue, chest pain, and syncope in advanced stages; may also present with leg edema and signs of right heart failure • Physical findings include loud P2 heart sound, right ventricular heave, and signs of right heart strain (e.g., jugular venous distension, peripheral edema)
- The pressure can become so great that the right heart can no longer pump against the vascular resistance, which leads to right heart failure and Cor Pulmonale
- Pulmonary Arterial Hypertension
- Pulmonary Hypertension due to left heart disease
- Pulmonary Hypertension due to lung disease
- Pulmonary Hypertension due to blood clots in the lungs
- Blood and other rare disorders that lead to Pulmonary Hypertension

The classic findings on chest radiography in a patient with pulmonary arterial hypertension include enlarged central pulmonary arteries that taper distally (peripheral pruning), attenuated peripheral vessels, and oligemic lung fields.
Pulmonary hypertension is difficult to diagnose early on as signs and symptoms are often related to the underlying cause
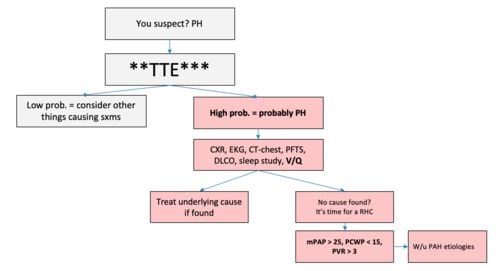
- Transthoracic echocardiogram (first diagnostic test for pulmonary HTN)
- Increased pressure in pulmonary arteries, right ventricles → dilated pulmonary artery
- Dilatation/hypertrophy of right atrium, right ventricle
- Large right ventricle → bulging septum
- Right heart catheterization is the GOLD STANDARD for diagnosis of pulmonary HTN → most accurate measure of pressures
- In pulmonary hypertension, the pressure increases > 20 mmHg at rest
- Chest X-Ray - The classic findings on chest radiography in a patient with pulmonary arterial hypertension include enlarged central pulmonary arteries that taper distally (peripheral pruning), attenuated peripheral vessels, and oligemic lung fields.
- ECG → Right heart strain pattern: T wave inversion in right precordial (V1–V4), and inferior leads (II, III, aVF)
Diagnostic algorithm for pulmonary hypertension
Identify and treat the underlying cause
- Pulmonary hypertension secondary to left ventricular failure → optimize left ventricular function
- Diuretics (cautiously—individuals may be preload dependent)
- Digoxin
- Anticoagulants
- Pulmonary arterial hypertension (WHO group 1) — confirmed by right heart catheterization
- Relax smooth muscle (promote vasodilation), reduce vascular remodeling, improve exercise capacity with prostanoids, phosphodiesterase inhibitors, endothelin antagonists
- Not used for pulmonary HTN due to left heart disease or lung disease (can worsen pulmonary edema or hypoxemia)
- PAH drug classes to know
- Endothelin receptor antagonists
- Prostanoids
 Osmosis |
|
 |
Question 1 |
Chronic thromboembolic disease Hint: Chronic thromboembolic pulmonary hypertension (group 4) follows prior pulmonary emboli and is diagnosed with a V/Q scan; nothing here suggests prior clots. | |
Idiopathic pulmonary arterial hypertension Hint: Idiopathic pulmonary arterial hypertension (group 1) is rare, typically affects younger women, and is a diagnosis of exclusion. | |
Left heart disease | |
Lung disease (COPD or interstitial lung disease) Hint: Pulmonary hypertension from lung disease (group 3) needs significant COPD, interstitial lung disease, or chronic hypoxemia, which she does not have. | |
Sarcoidosis Hint: Sarcoidosis is a group 5 cause and would show lung or systemic findings. |
Question 2 |
Chest radiograph Hint: A chest radiograph can show enlarged central pulmonary arteries but cannot measure pressures. | |
CT pulmonary angiography Hint: CT pulmonary angiography looks for acute pulmonary emboli; it does not measure pulmonary artery pressure. | |
Pulmonary function testing Hint: Pulmonary function tests look for an underlying lung cause but do not confirm pulmonary hypertension. | |
Right heart catheterization | |
Ventilation-perfusion scan Hint: A V/Q scan screens for chronic thromboembolic pulmonary hypertension once pulmonary hypertension is suspected; it does not confirm the diagnosis. |
Question 3 |
Ambrisentan plus tadalafil | |
Amlodipine Hint: High-dose calcium channel blockers are reserved for the small group with a positive vasoreactivity test; they can be harmful in nonresponders. | |
Furosemide alone Hint: Diuretics treat fluid retention from right heart failure but do not treat the pulmonary vasculopathy. | |
Metoprolol Hint: Beta-blockers have no role in pulmonary arterial hypertension and can worsen right ventricular function. | |
Warfarin Hint: Routine anticoagulation is no longer recommended for most patients with idiopathic pulmonary arterial hypertension. |
Question 4 |
Greater than 10 mm Hg Hint: A normal resting mean pulmonary arterial pressure is about 8 to 20 mm Hg, so 10 mm Hg is within the normal range. | |
Greater than 15 mm Hg Hint: A mean pulmonary arterial pressure of 15 mm Hg is normal. | |
Greater than 20 mm Hg | |
Greater than 25 mm Hg Hint: 25 mm Hg was the older threshold. The current definition uses a mean pulmonary arterial pressure greater than 20 mm Hg. | |
Greater than 30 mm Hg Hint: 30 mm Hg is well above the diagnostic threshold; using it would miss patients with mild pulmonary hypertension. |
Older definitions used a threshold of 25 mm Hg or greater, so 25 mm Hg is the classic trap. Echocardiography can estimate pulmonary pressures and screen for the disease, but right heart catheterization is required to confirm the diagnosis.
|
List |
References: Merck Manual · UpToDate